Diabetes can affect oral health, especially the gums, and treatment planning should reflect the person’s current health status. The dentist needs an up-to-date picture of the person’s glucose management, medicines, meal timing, complications and planned procedure. Most people with stable diabetes can receive routine dental care; extra planning matters when diabetes is unstable, hypoglycemia is likely, or surgery will disrupt eating.

What diabetes means for dental care
Diabetes mellitus describes conditions in which blood glucose remains higher than usual because the body makes too little insulin, cannot use insulin effectively, or both. Type 1 diabetes results from autoimmune destruction of insulin-producing beta cells and can begin at any age. Type 2 diabetes is much more common and involves insulin resistance and progressive difficulty making enough insulin; it can occur in younger as well as older people. Avoid treating age or body size as a diagnosis. The CDC overview of diabetes explains the main types and risk factors.
Diabetes care can involve insulin, medicines that lower glucose, glucose monitoring and individualized food or activity plans. The details vary widely. A dentist should not tell a patient to skip a meal, change an insulin dose or stop another medicine without a coordinated plan from the prescribing clinician. The aim is to keep care predictable and reduce avoidable changes in food intake, stress, pain or medication timing.
Oral conditions associated with diabetes
Periodontitis is the best-established oral-health concern. It damages the tissues and bone that support teeth and can lead to tooth mobility or loss if disease progresses. People with diabetes, particularly when glucose is poorly controlled, have higher average prevalence and severity of periodontal disease. A fixed “three times the risk” figure should not be applied to every person. Risk also depends on smoking, plaque, prior periodontal disease, access to care and other health factors.
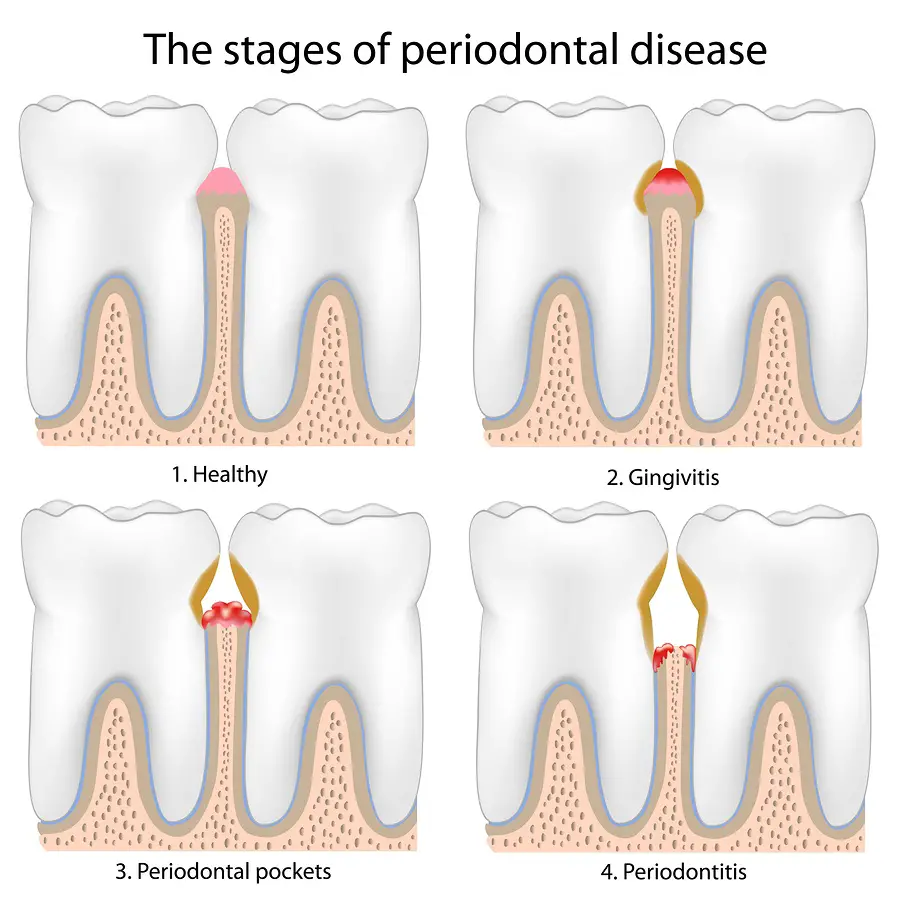
Diabetes and periodontitis are commonly described as having a bidirectional relationship: hyperglycemia can worsen periodontal risk, while periodontitis is associated with poorer glycemic control. Periodontal treatment improves gum health and is part of good diabetes care, but it is not a substitute for diabetes treatment. Research suggests periodontal therapy may modestly improve A1C for some people, although clinical trials have not shown a uniform effect. The American Dental Association’s diabetes guidance recommends considering individual status and coordinating care where needed.
Dry mouth is another possible concern. It may reflect poor glucose control and dehydration, but medications, neuropathy, salivary-gland changes and other conditions can contribute. Reduced saliva can make speaking, swallowing or denture use uncomfortable and may raise cavity risk. Diabetes itself does not guarantee more cavities: risk depends on dry mouth, frequent sugar exposure, plaque control, fluoride and other local factors. Learn about dry mouth causes and care.
Oral candidiasis can be more likely when diabetes is poorly controlled, especially alongside dry mouth, dentures, recent antibiotics or inhaled corticosteroids. A white coating, soreness or burning needs assessment because several conditions can look similar. Burning-mouth symptoms have many causes; diabetes or neuropathy may contribute in some people, but burning is not a stand-alone sign that diagnoses diabetes. Delayed healing and infection concerns are also more relevant when glucose is persistently high, but they do not mean every person with diabetes will heal poorly.
Caries risk should be assessed individually. Dry mouth, exposed root surfaces, frequent sweet drinks or snacks and difficulty cleaning can increase risk. Twice-daily fluoride brushing and daily interdental cleaning remain useful. A dentist can consider additional fluoride or other prevention based on the patient’s examination. Our guides cover diabetes and oral health, gingivitis and periodontal disease, and daily oral hygiene.
Plan the visit with the patient’s usual routine in mind
Before treatment, the dental team should review diabetes type, medicines and dosing schedule, usual glucose-monitoring plan, recent hypoglycemia, the most recent A1C when relevant, meal timing and diabetes-related complications. Kidney disease, cardiovascular disease, neuropathy, eye problems and impaired mobility can change how care is delivered or which medicines are appropriate. An A1C is one part of the picture; it should not replace a conversation about current stability and the procedure.
- Bring a current list of prescription medicines, over-the-counter products and allergies.
- Tell the dentist about recent low-glucose episodes, the usual monitoring routine and any relevant recent A1C result.
- Describe usual meal timing and whether sedation, fasting or recovery is expected to change food intake.
- Mention kidney, heart, nerve, vision or healing complications that could affect treatment.
Morning visits may suit some people, but the best time depends on usual meals, medicine timing and peak insulin activity. The ADA advises avoiding appointments that coincide with peak insulin action when that would raise hypoglycemia risk. Patients should generally eat normally and take prescribed medicines before routine care unless a clinician has provided different instructions. If sedation, fasting or surgery will affect food intake, the dental and medical teams should agree on a medication and nutrition plan beforehand.
Recognize and respond to hypoglycemia
Hypoglycemia is low blood glucose. It can occur when insulin or another glucose-lowering medicine has more effect than expected, a meal is skipped or delayed, or physical activity changes. In a dental office, altered food intake or a long appointment can be part of the problem. Common signs include shakiness, sweating, hunger, a fast heartbeat, dizziness, weakness, behavior change, irritability, blurred vision, poor coordination or confusion. Severe hypoglycemia can cause seizure or unconsciousness. Red, dry skin, rapid breathing and fruity breath are not the typical symptom list for low glucose; they can signal another urgent problem.
- Check glucose with a meter when available and follow the dental office emergency protocol.
- If the patient is alert and can swallow, give about 15 g of fast-acting glucose or carbohydrate.
- Recheck after 15 minutes and repeat treatment if glucose remains low; call emergency services if the patient is not alert, cannot swallow or worsens.
Never give food, drink or oral glucose gel to someone who is unconscious, having a seizure or unable to swallow safely. Call emergency medical services and follow the practice’s emergency protocol. A trained team may use glucagon if available and indicated. Syncope and hypoglycemia can overlap; chair position alone does not reliably distinguish them. Check glucose when low blood sugar is plausible and escalate promptly if the person’s condition does not improve.
Recognize a different kind of emergency
Marked hyperglycemia with vomiting, abdominal pain, dehydration, rapid or labored breathing, confusion or fruity-smelling breath can indicate diabetic ketoacidosis or another acute illness. These symptoms need urgent medical evaluation, not dental-office attempts to manage glucose. If symptoms are severe or the patient is rapidly worsening, call emergency services.
Surgery, antibiotics and medicines
Many people with stable diabetes can undergo common dental procedures conventionally. Extensive surgery, sedation, unstable glucose, active infection or significant complications may call for coordination with the patient’s physician. If recovery will restrict food, establish how the patient will maintain nutrition and follow their medication plan. A dentist should explain the expected diet and warning signs; diabetes medicines should not be changed without the prescriber’s guidance.
Diabetes alone does not mean a person needs preventive antibiotics before or after dental treatment. Antibiotics are used when there is a clinical indication, such as a bacterial infection, and the decision depends on the procedure and the patient’s circumstances. A blanket instruction to “aggressively treat” every acute infection can encourage unnecessary medication; prompt diagnosis and appropriate treatment are the goal.
Kidney disease and other diabetes complications can affect safe prescribing. Do not assume that one pain medicine or antibiotic is right for every person. The clinician should consider kidney function, allergies, other medicines and the specific procedure when selecting a drug and dose. Patients should tell the dental team about prescription medicines, nonprescription pain relievers and supplements. For more context, see our guide to analgesics in dental practice.
A previous heart attack or stroke also should not be reduced to a blanket “emergency dentistry only for six months” rule. Current cardiovascular stability, medicines, procedure and medical guidance determine timing. The dentist may coordinate with the treating clinician for a recent or unstable event, but the decision is individualized.
How often should people with diabetes see a dentist?
There is no requirement that every patient with diabetes have a dental cleaning every three months. Recall and periodontal-maintenance intervals depend on active gum disease, caries risk, dry mouth, smoking, glucose stability, home-care ability and how the person responds to treatment. Some patients with active periodontitis benefit from shorter maintenance intervals; others may not need that schedule. The dentist should explain the reason for the interval and adjust it as findings change.
Between visits, brush twice a day with fluoride toothpaste and clean between teeth daily using a method that works for the person. Tell the dentist about recurrent gum bleeding, swelling, persistent dry mouth, sore areas, dentures that rub or a sudden change in bite. Dental teams may notice signs or risk factors that warrant medical screening, but oral findings do not diagnose diabetes. Diagnosis requires appropriate clinical and laboratory testing.
- Brush twice daily with fluoride toothpaste and clean between teeth once daily.
- Ask whether dry mouth or root exposure calls for extra fluoride or another preventive measure.
- Schedule follow-up based on gum and tooth findings and the response to care.
For additional support, read our information on oral signs associated with diabetes, dry mouth, and gum disease prevention and care. People with new or worsening symptoms should seek individualized advice from a dentist or physician.
Common questions
Takeaway
Diabetes can increase periodontal risk and may affect dry mouth, infection and healing, particularly when glucose is poorly controlled. It does not make dental treatment unsafe by default. Good care begins with a current medical history and a plan that respects the patient’s meals, medicines and procedure. Dental teams should recognize hypoglycemia, avoid rigid glucose cutoffs and recall schedules, and coordinate when diabetes is unstable or surgery changes eating. These steps support oral health without promising that periodontal treatment will control blood glucose.