Supplements and molecules · evidence reviewed September 2026
What NMN is
Nicotinamide mononucleotide, usually abbreviated NMN, is a nucleotide-related intermediate in the biosynthesis of nicotinamide adenine dinucleotide, or NAD+. NAD+ is used in redox metabolism and in signaling reactions involving enzymes such as sirtuins and PARPs. NMN is therefore studied as a possible way to increase the availability of NAD-related molecules.
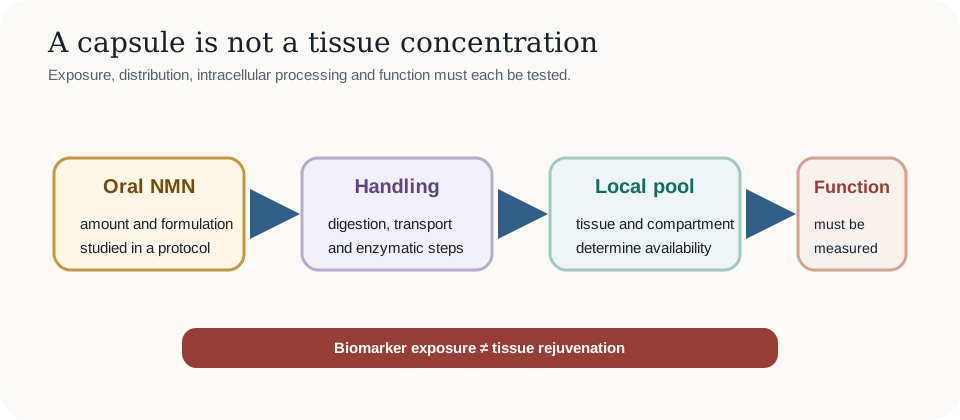
NMN is not NAD+ itself and it is not a complete explanation for age-related metabolic change. After oral intake, NMN is handled by digestion, transport, cellular uptake and multiple enzymatic steps. Its final effect depends on tissue, dose, formulation, baseline metabolism and the balance between NAD+ production and consumption.
The distinction matters because supplement marketing often compresses a long biochemical chain into “more NAD equals younger cells.” A scientifically bounded review follows the chain and asks what was actually measured in humans.
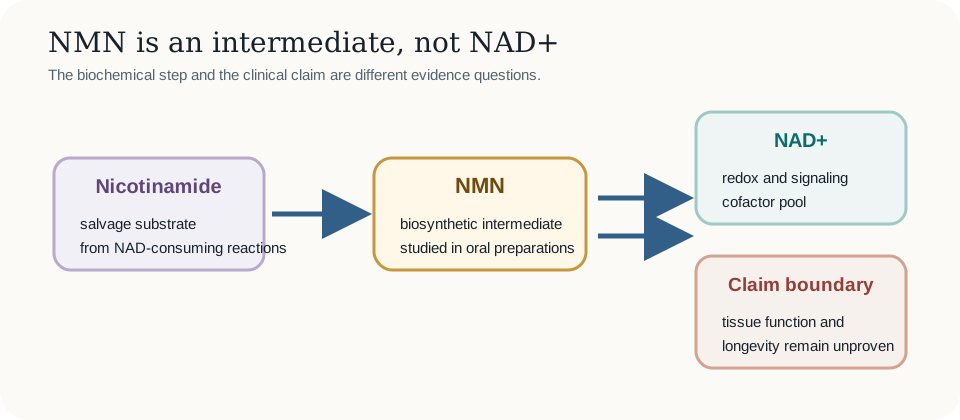
How NMN enters NAD+ metabolism
In the salvage pathway, nicotinamide can be converted to NMN and then to NAD+. This makes NMN an attractive research compound because it sits close to NAD+ in one biosynthetic route. The pathway is not a one-way pipe, however. Enzyme activity, substrate availability, compartmentalization and NAD-consuming reactions determine how much of an administered precursor contributes to a particular cellular pool.
NMN can also be converted or transported in ways that differ between tissues and species. The concentration in a capsule is not the concentration in a human mitochondrion, muscle fiber or neuron. Pharmacokinetic studies are useful because they test exposure and distribution; they do not automatically establish a clinical effect.
For the parent biology, see NAD+ metabolism and aging. It explains why blood or peripheral-cell measurements can show target engagement while leaving the function of other tissues uncertain.
NMN versus NAD+ itself
NMN and NAD+ are chemically related but pharmacologically different. NAD+ is a larger cofactor used inside cells, while NMN is a biosynthetic intermediate that must be processed or transported before it contributes to an NAD pool. A study of oral NMN should not be described as a study of oral NAD+ and should not be generalized to intravenous NAD+.
Direct NAD+ infusions are also a separate evidence question. A 2026 systematic review of NAD-related supplementation found no eligible human outcomes trials evaluating intravenous or intramuscular NAD+ itself for anti-aging or wellness indications. Short-term pharmacokinetic observations cannot fill that clinical gap.
Why NMN became a longevity supplement
NMN attracted attention because aging research links NAD metabolism with mitochondrial function, DNA-damage responses, sirtuins, inflammation and energy sensing. Rodent studies often report improved metabolic or functional measures after NAD augmentation. These mechanisms create a credible reason to run human trials, but they are not a guarantee that the same dose, tissue exposure or endpoint will translate.
Commercial interest grew faster than the clinical evidence. A compound can be scientifically interesting and still have an uncertain benefit-risk profile outside the studied setting. Product labels may use “anti-aging,” “cellular energy” or “longevity” language that goes beyond the endpoints actually tested.
Our linked pages on sirtuins and aging, mitochondrial dysfunction and AMPK and aging show why a plausible network should be treated as a research rationale, not as proof for a supplement claim.
Animal lifespan and healthspan evidence
In mice and other experimental systems, NAD-related interventions have been associated with changes in metabolism, inflammation, mitochondrial function and selected age-related phenotypes. These studies can identify mechanisms, timing questions and candidate outcomes. Some report lifespan or healthspan effects under particular laboratory conditions.
Animal results are not direct evidence of human lifespan extension. Species differ in metabolism, diet, housing, disease spectrum and exposure. A rodent dose may produce a tissue concentration or pharmacology that cannot be reproduced safely in people. Even a positive mouse result may depend on sex, strain, age at treatment and baseline health.
The correct interpretation is therefore “preclinical support for further testing.” It is not “NMN extends human life,” and it does not establish a recommended dose.
Human trials: NAD target engagement
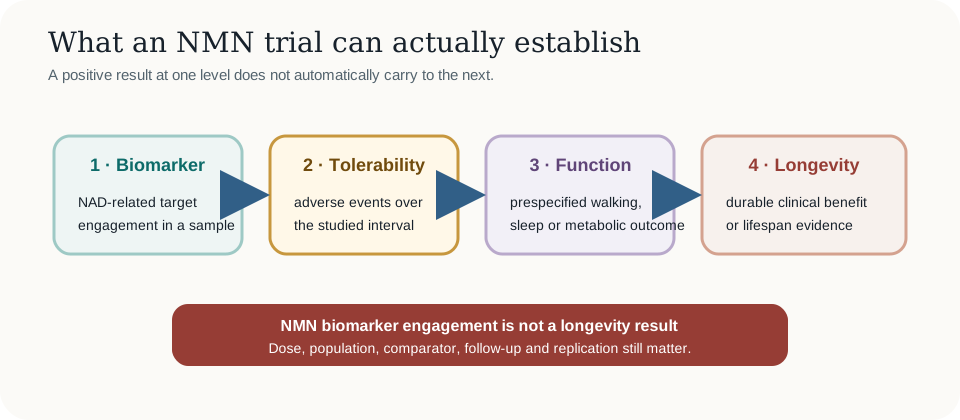
The most consistent human finding is biochemical. Oral NMN can increase blood NAD+ or related metabolites over the studied interval, and some trials measure changes in peripheral cells or other samples. This shows that the preparation was absorbed and biologically active enough to alter a measured pathway.
Target engagement is an important step, but it is not the same as clinical efficacy. A blood response does not prove that the brain, muscle, liver or a mitochondrial compartment changed in the intended way. The 2026 systematic review of NAD+ supplementation found consistent biochemical engagement for oral NR and NMN while functional, metabolic, vascular and other healthspan results were heterogeneous and often null or endpoint-specific.
Trials should report the assay, sample type, timing, baseline health and whether the biomarker was primary or exploratory. A larger change in a surrogate is not automatically a larger health benefit.
| Result | Supported interpretation | Unsupported leap |
|---|---|---|
| Blood NAD-related increase | Biochemical target engagement in the sampled compartment. | Whole-body rejuvenation. |
| Change in a secondary measure | A signal needing prespecified and replicated testing. | Proof of the product’s primary benefit. |
| No primary endpoint difference | No demonstrated benefit for that outcome and study design. | Calling a favorable biomarker a clinical success. |
| Short-term tolerability | No clear excess harm over the reported interval. | Long-term safety for every user. |
Human trials: physical function and walking
A randomized, double-blind, placebo-controlled study in 60 older adults examined 250 mg/day of NMN for 12 weeks. The primary stepping-test outcome did not differ significantly between the NMN and placebo groups at the prespecified time points. Selected secondary findings included a shorter four-metre walking time, higher blood NAD-related measures and better scores on some sleep measures after 12 weeks.
This is a useful example of how to read a trial without flattening its results. The primary endpoint and the secondary endpoints are not interchangeable. The study was relatively short and small, so it can inform target engagement and generate hypotheses about walking or sleep without proving a durable functional or longevity benefit.
The authors reported no adverse effects related to the test substance in that study, and some authors were employees of the product manufacturer’s parent company. That does not invalidate the findings; it is relevant context for replication and interpretation.
Human trials: metabolic, vascular, sleep and exploratory outcomes
Across human studies, NMN has been tested against a range of metabolic, vascular, sleep, fatigue and physical-performance measures. Results differ by age, baseline metabolic risk, study duration, formulation and endpoint. A favorable change in one secondary measure can coexist with no change in the primary outcome or with no change in related measures.
The 2026 NMN safety and metabolism meta-analysis included 15 trials, with 10 contributing to safety analyses. Reported doses ranged from 250 to 2,000 mg/day and durations from 14 days to 24 weeks. The review found no significant increase in overall, serious or withdrawal-related adverse events and no significant rise in ALT or AST, while broad benefits on body weight, BMI, fasting glucose, HbA1c, lipids or systolic blood pressure were not evident. A small diastolic-blood-pressure signal and a nonsignificant HOMA-IR trend were described as preliminary, not definitive.
Those numbers describe the included research, not a dosing plan. The evidence remains limited by short follow-up, heterogeneous preparations and the number of participants available for different outcomes. A meta-analysis can summarize existing trials; it cannot create evidence that the trials did not collect.
- Separate the primary endpoint from exploratory measures.
- Check whether the result was statistically and clinically meaningful.
- Look for replication outside the same research group or product family.
- Read follow-up duration and withdrawals before generalizing safety.
Doses studied in human trials
Human NMN trials have studied different oral amounts and schedules. The older-adult walking and sleep study used 250 mg/day for 12 weeks. The 2026 safety meta-analysis reported included study doses from 250 to 2,000 mg/day, with durations from 14 days to 24 weeks. These are descriptive ranges from research protocols, not recommended doses.
Comparing milligrams across products can be misleading. Purity, formulation, co-ingredients, storage, adherence and analytic verification affect what participants actually receive. A dose studied in a controlled trial cannot be assumed to have the same identity or exposure as an online product.
| Report | Why it matters | Do not infer |
|---|---|---|
| Amount and frequency | Defines the exposure tested in the protocol. | A universal personal dose. |
| Duration | Sets the boundary for safety and efficacy evidence. | Long-term tolerability. |
| Preparation | Identifies purity, formulation and co-ingredients. | Equivalence between brands. |
| Population | Shows whose response was measured. | Same effect in every age or disease group. |
Safety, adverse events and study duration
Short oral NMN trials have generally reported favorable tolerability, and the 2026 meta-analysis did not find a clear increase in overall, serious or withdrawal-related adverse events or liver-enzyme abnormalities within its included studies. That is reassuring but bounded evidence. Most trials were short, and absence of a detected signal is not proof of safety for indefinite use or for every medical context.
Potential risks also include product contamination, inaccurate labeling, interactions with medicines and the possibility that a biologically active pathway has different effects in a particular disease. Evidence about cancer biology, pregnancy, liver or kidney disease and complex medication regimens should not be improvised from a supplement article.
Study duration is central. Fourteen days to 24 weeks can identify short-term tolerability and some intermediate outcomes, but it cannot establish whether an intervention prevents dementia, cardiovascular disease, frailty or death. Longer and larger trials with prespecified clinical endpoints are needed.

NMN versus NR
NMN and nicotinamide riboside, or NR, are both NAD precursors, but they differ in chemistry, transport, formulation and the human studies available. A higher biomarker response for one preparation in one trial does not prove that it is clinically superior to the other. Cross-trial comparisons are especially vulnerable to differences in population, assay and duration.
The 2025 human review of NAD precursor supplementation emphasizes that evidence for age-related NAD decline is limited in humans and that clinical efficacy remains modest or uncertain. Our NR and longevity guide and NMN versus NR comparison should be read alongside new randomized evidence rather than as fixed product rankings.
Both compounds should be judged by the same hierarchy: verified exposure, relevant target engagement, primary functional outcomes, durable safety and replication. Marketing claims should not decide the comparison before the endpoints do.
Regulatory and product-quality considerations
Regulatory status depends on jurisdiction, product identity, intended use and the claims made on the label. Current status: in Canada, Health Canada states that natural health products require product licensing before sale and that licensed products carry an eight-digit Natural Product Number. A license indicates authorization for the labeled conditions of use; it is not evidence that NMN extends lifespan or that every product sold online is licensed.
Consumers should be able to identify the ingredient amount, lot information, manufacturer, storage instructions and applicable authorization. Independent testing can help with identity and contamination questions, but a certificate of analysis does not prove clinical efficacy. Products with blends or undisclosed amounts make trial comparisons harder.
Regulatory rules change, so this section must be rechecked before publication and whenever a regulator issues a new decision. Do not infer legality, safety or efficacy from a product’s availability in an online marketplace.
- Check the applicable regulator and product-license database.
- Match the label to the preparation studied in the cited trial.
- Look for clear amounts, lot traceability and contaminant testing.
- Separate authorization for sale from proof of a longevity effect.
What NMN has not been shown to do
NMN has not been shown in adequately powered long-term human outcomes trials to slow biological aging, extend human lifespan, reverse mitochondrial aging, prevent multiple age-related diseases or replace established treatment. It has also not been established that increasing blood NAD+ improves every tissue or that a commercially available product reproduces a research preparation.
These limits are not an argument that NMN research should stop. They are the reason the next studies should be designed around clinically meaningful questions. A biomarker response can justify a larger trial; it cannot be promoted as the result of that trial.
Evidence verdict and unanswered questions
Oral NMN is a biologically active NAD precursor. Human trials support increases in NAD-related biomarkers and generally favorable short-term tolerability. Evidence for walking, sleep, metabolic, vascular or other functional benefits is mixed, often endpoint-specific and not sufficient to claim slowed aging or human lifespan extension.
The most important unanswered questions concern tissue distribution, long-term safety, clinically meaningful endpoints, product equivalence and which populations—if any—benefit. Future trials should be larger, longer, independently replicated and transparent about primary outcomes, adverse events, funding and preparation quality.
Until that evidence exists, NMN is best described as a promising research compound and supplement ingredient with demonstrated target engagement, not as a proven anti-aging therapy.