What creatine is and why aging changes the question
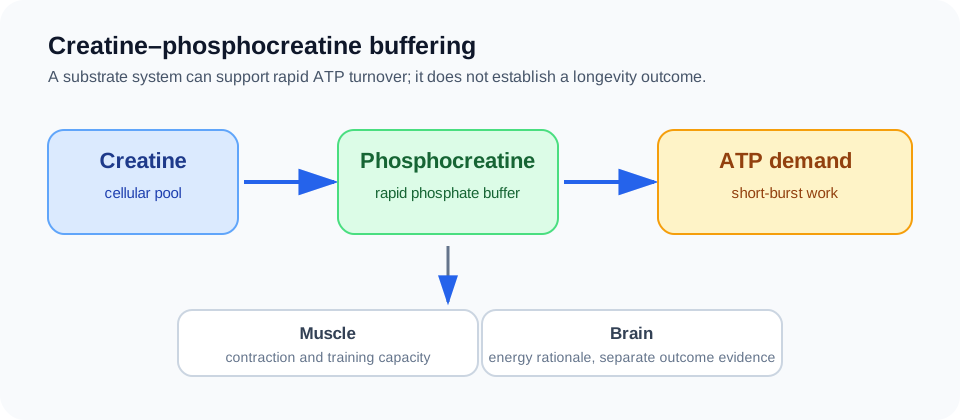
Creatine is a naturally occurring compound obtained from food and synthesized in the body. Creatine and phosphocreatine help buffer rapid energy demand, especially in skeletal muscle and other tissues with high or fluctuating ATP requirements. Supplementation increases creatine stores; for older adults, the key question is whether added creatine improves an outcome that matters—strength, lean tissue, physical function, cognition or quality of life.
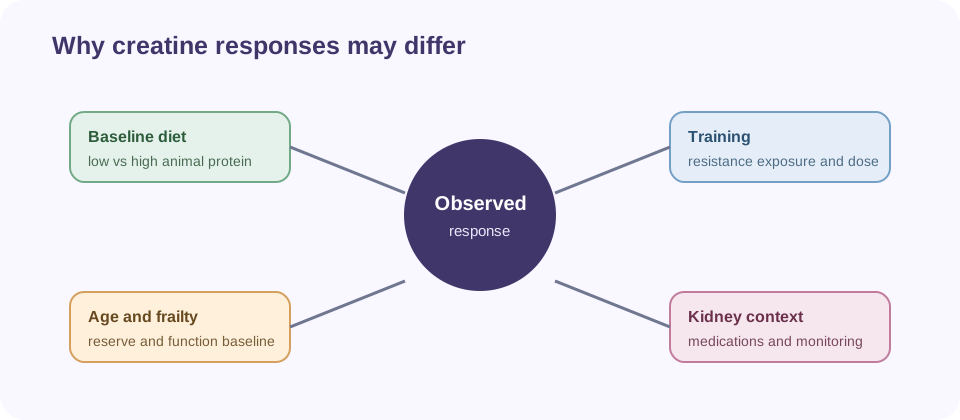
Aging changes that question because muscle mass, power, training exposure, dietary intake, activity, illness and recovery capacity vary widely. An older adult who is already training, eating adequately and maintaining muscle may respond differently from someone with inactivity, low protein intake, chronic disease or an impending period of rehabilitation. Age alone does not determine benefit.
The creatine and longevity page places the supplement in the wider evidence map. This page narrows the question to older-adult outcomes and keeps function, safety and lifespan claims separate.
Phosphocreatine, ATP buffering and skeletal muscle
During brief, high-intensity effort, phosphocreatine can donate a phosphate group to help regenerate ATP. That energy-buffering system is relevant to repeated contractions, resistance exercise and high-power tasks. Supplementation may make it easier to perform or recover from some training work, which is one plausible route to greater adaptation over time.
The mechanism does not mean that every older adult will gain the same amount of muscle. Training stimulus, adherence, baseline creatine stores, nutrition, sleep, illness and the way an outcome is measured all matter. Mechanistic plausibility explains why trials are worth doing; it cannot substitute for randomized comparisons.
Creatine is also found in brain tissue, which is why researchers have studied memory, attention and executive function. Brain uptake, dietary pattern and task demands may influence a response, but the presence of creatine in the brain does not establish that oral supplementation treats cognitive impairment.
| Observed outcome | Reasonable interpretation | Claim it cannot support alone |
|---|---|---|
| Lean tissue mass | body-composition change under a specific protocol | stronger mobility or lower disability risk in every user |
| 1RM or grip strength | performance on a tested task | prevention of falls, frailty or disease |
| Memory or attention task | possible domain-specific cognitive signal | dementia prevention or treatment |
| Biochemical marker | pharmacologic or physiologic response | longer healthspan or lifespan |
Why resistance training remains the foundation
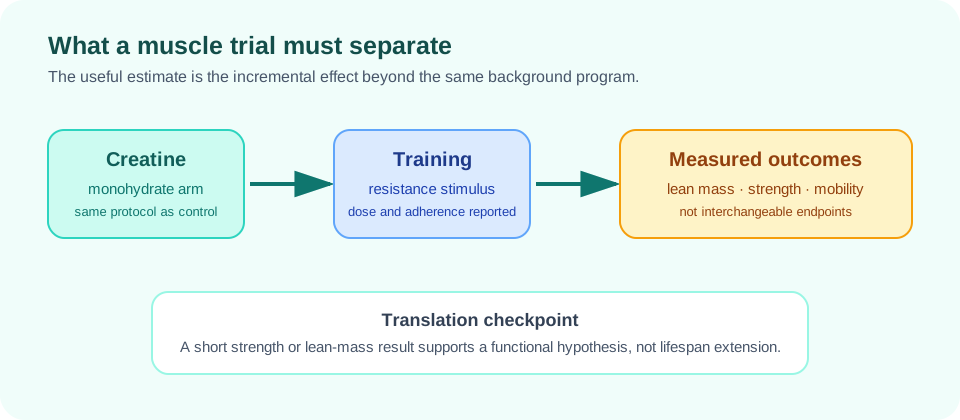
The clearest aging-relevant creatine evidence usually comes from studies in which supplementation is added to resistance training. That design matters: the exercise program supplies a repeated stimulus for muscle adaptation, while creatine may help support training volume, recovery or short-duration performance. It is therefore misleading to describe the result as a supplement acting independently of exercise.
Resistance training also has benefits that do not depend on creatine: improved strength, power, balance and confidence with movement, depending on the program and participant. Creatine can be an adjunct, not a replacement for a safe, progressive plan. For an older adult with pain, falls, major weakness, recent surgery or chronic disease, exercise selection and supervision may be more important than the choice of supplement.
The practical comparison in many trials is creatine plus exercise versus placebo plus exercise. The question is the incremental effect. It is not creatine versus doing nothing.
What the 2025 meta-analyses found in older adults
A 2025 systematic review and meta-analysis of creatine plus resistance training included eight randomized trials and 482 participants. Compared with placebo plus resistance training, the pooled analysis found a small improvement in lower-limb strength (standardized mean difference 0.29; 95% confidence interval 0.00 to 0.57) and lean tissue mass (standardized mean difference 0.27; 95% confidence interval 0.02 to 0.53). Upper-extremity strength was not significant in the overall analysis, although shorter interventions of up to 32 weeks showed a stronger upper-limb subgroup signal. These are average effects across selected trials, not a guaranteed result for an individual.
A second 2025 review synthesized 20 articles and 1,093 older participants, 69% of whom were women. Creatine plus exercise was associated with a mean difference of 2.122 kg in a pooled 1RM analysis and a small reduction in body-fat percentage. The same review found no significant effect on total-body bone mineral density. Its exercise and participant mix was broad, so the pooled number should not be read as a universal dose-response estimate or a direct measure of mobility.
Meta-analysis improves precision but does not remove limitations in the included studies. Protocols differ in dose, training mode, duration, adherence, age, sex, baseline diet and outcome measurement. Some analyses also contain small studies, subgroup results and endpoints that are surrogates for everyday function.
Lean mass: magnitude and clinical relevance
Older-adult trials have reported increases in lean tissue mass with creatine and resistance training. A commonly cited earlier meta-analysis found an additional mean difference of about 1.37 kg during resistance training, while the newer 2025 review reported a smaller standardized effect. The difference illustrates why readers should not lift one number out of a pooled analysis: study selection, outcomes and analytic methods change the estimate.
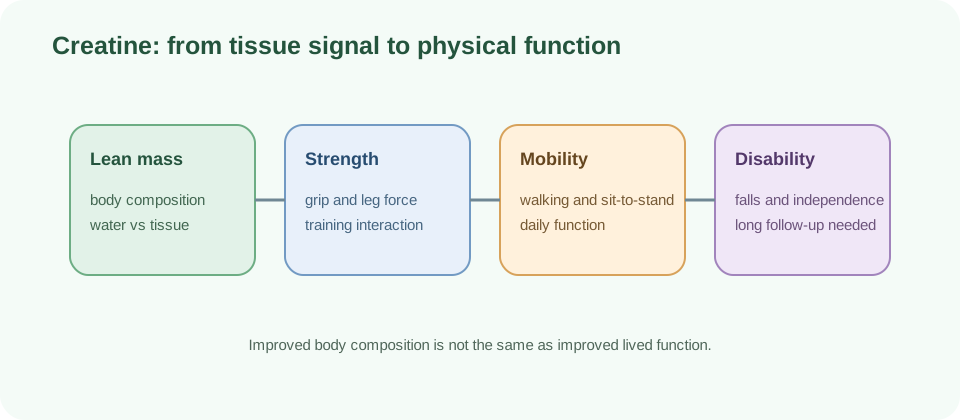
Lean mass measured by DXA or another body-composition method is not identical to contractile muscle, and early weight gain can include water associated with increased creatine storage. A larger lean-mass value may still be useful, but it should be interpreted with strength, power, walking, chair-rise performance and the person’s goals.
For sarcopenia, diagnosis and management require more than a supplement response. The relevant questions include muscle strength, physical performance, nutrition, underlying disease, medication effects and progressive loss over time. The sarcopenia and muscle aging page covers that broader assessment boundary.
Upper- versus lower-body strength findings
Strength results are not uniform across body regions. The 2025 creatine-plus-resistance-training meta-analysis found a statistically significant lower-limb signal in its overall analysis, while the upper-limb result was not significant overall. Its duration subgroup suggested better upper-limb gains in interventions lasting up to 32 weeks, but subgroup findings are more fragile than the main comparison and should be treated as hypothesis-generating.
Another 2025 exercise meta-analysis found a significant pooled 1RM result, yet its subgroup pattern showed that some exercises, including leg press and lat pull-down, drove the association while arm curl, bench press and chest press were not individually significant. A pooled strength result does not mean every movement improves.
Testing also matters. A one-repetition maximum is a trained performance measure that can be affected by technique and familiarization. Grip strength is clinically useful but can be influenced by pain, hand dominance and motivation. Everyday function is important, but many supplement trials are too short or small to establish effects on falls, independence or disability.
Physical function and disability-risk evidence
A 2024 systematic review and meta-analysis examined creatine trials in older adults and adults with chronic disease at risk of functional disability. Across 33 randomized trials and 1,076 participants, six trials reporting sit-to-stand produced a pooled standardized mean difference of 0.51, with a wide confidence interval from 0.01 to 1.00 and substantial heterogeneity. Upper-body strength, handgrip strength and lean tissue mass also favored creatine in pooled analyses.
The authors graded the evidence as low or very low quality because of risk of bias. The review is therefore useful for showing a signal worth testing, not for proving that creatine prevents disability. A study that measures a faster chair-rise test after a short intervention does not establish fewer falls or delayed nursing-home admission.
Function-focused trials should report baseline frailty, training exposure, adherence, adverse events and absolute changes. They should also distinguish participants who are healthy and community-dwelling from those in rehabilitation or living with chronic disease. Those populations have different baseline risks and different reasons to consider supplementation.
Postmenopausal women: the 2026 evidence update
A 2026 systematic review and meta-analysis focused on postmenopausal women included seven randomized trials and 608 randomized participants, with a median intervention duration of 38 weeks. Creatine favored lean mass by 0.37 kg (95% confidence interval 0.05 to 0.69) and leg-press 1RM by 7.5 kg (95% confidence interval 2.2 to 12.8). The authors reported that benefits were most evident when at least 5 g per day was combined with resistance training, while lower-dose studies without resistance training did not show a measurable effect.
Bone density was unchanged overall, and the review’s prediction interval for lean mass crossed no effect. Adverse events were mild and similar to placebo in the included trials, with renal indices unchanged. That finding is reassuring within the studied populations and follow-up; it is not a guarantee for someone with kidney disease, complex medication use or acute illness.
The review also had limitations: risk of bias was mostly rated as “some concerns,” it was not prospectively registered, and the sample sizes were modest. Sex- and cohort-specific evidence is valuable because it tests whether an average effect is consistent in a group with distinct muscle and bone changes, but it does not eliminate the need for individualized clinical assessment.
| Question | Current evidence signal | Boundary |
|---|---|---|
| Lean mass | small additional gain with training in pooled trials | measurement is not the same as contractile muscle or mobility |
| Strength | some lower-limb and selected 1RM outcomes improve | not every exercise or subgroup shows benefit |
| Physical function | sit-to-stand and grip signals are promising | evidence quality is low or very low in key synthesis |
| Bone density | no consistent pooled improvement | creatine should not be marketed as a bone-density treatment |
| Cognition | limited positive association, especially memory and attention | few trials, mixed methods and no dementia-prevention proof |
Bone outcomes: what remains uncertain
Bone is often included in creatine marketing because resistance training is relevant to skeletal loading and older adults face declining bone density. The current evidence does not justify a strong bone claim. The 2025 older-adult exercise meta-analysis found no significant effect on total-body bone mineral density, and the 2026 postmenopausal-women review reported no overall change in bone density.
There are still plausible reasons to study the combination: stronger muscles may support training, balance and load tolerance, while exercise itself may influence bone. But indirect support is not the same as a direct anti-osteoporosis effect. Bone outcomes need appropriate sites, sufficient duration, validated measurement and a population at relevant fracture risk.
Creatine and cognition in older adults
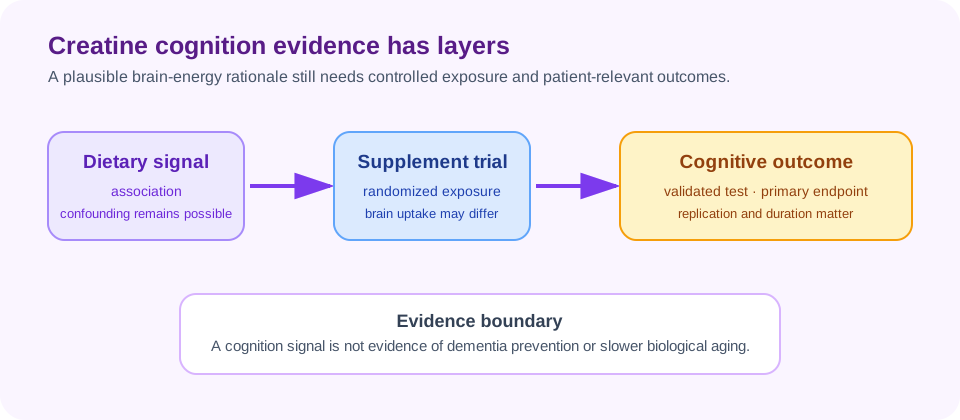
The 2026 systematic review of cognition in adults aged 55 and older included six studies with 1,542 participants, 55.7% of them women. Two studies were double-blind creatine interventions; four were cross-sectional studies that estimated dietary creatine by recall. Five of six studies reported a positive relationship, particularly for memory and attention, but the methodological ratings were one good, two fair and three poor.
This is a promising but limited evidence base. Dietary recall cannot prove that creatine caused a cognitive outcome, and an intervention that combines creatine with other changes cannot isolate the supplement. A positive result on a memory task may also be domain-specific and may not translate to clinically meaningful protection from cognitive decline.
A 2024 systematic review of creatine and cognition likewise described brain creatine increases but equivocal cognitive results, with design and dosing issues requiring better research. The current evidence supports carefully designed trials in people with low dietary creatine, sleep loss or cognitive vulnerability; it does not support presenting creatine as dementia prevention. The brain aging page explains why cognition claims require that distinction.
Sleep deprivation, low dietary creatine and vegetarian status
Creatine has been studied as a possible modifier of cognitive stress, including sleep deprivation, and as a potentially relevant supplement for people whose diets contain little or no meat or fish. These hypotheses are biologically plausible because dietary intake contributes to creatine availability, but plausible modifiers are not proven responder categories.
Dietary pattern can correlate with many other factors, including protein intake, education, socioeconomic conditions, exercise and overall diet quality. A vegetarian or vegan status does not identify a deficiency that can be diagnosed from a label alone. Similarly, one night of poor sleep does not establish that a supplement will restore performance.
Future trials should measure baseline diet, body composition, brain or blood creatine where appropriate, sleep, training, medication use and prespecified cognitive outcomes. Until then, the safe conclusion is that these factors may help explain heterogeneous results and deserve research.
Kidney-function myths versus appropriate medical caution
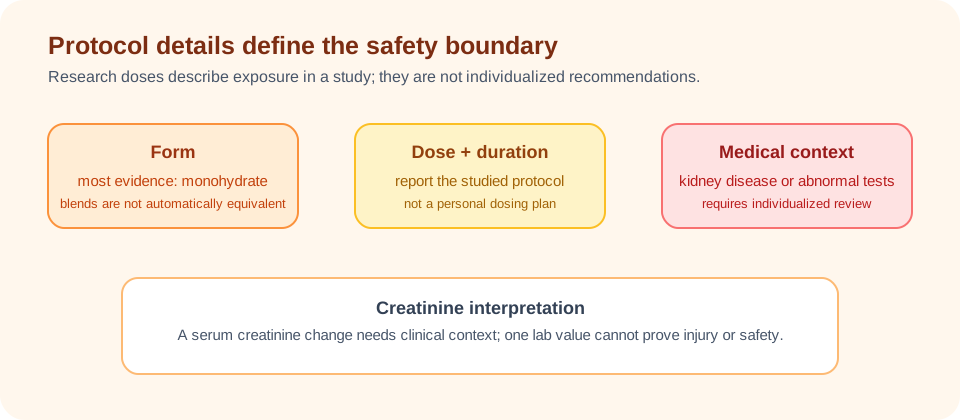
Creatine is converted to creatinine, a marker used in kidney assessment. Supplementation can change serum creatinine in some people without necessarily indicating a fall in filtration, which can complicate interpretation. That nuance is not permission to dismiss an abnormal result: kidney function must be interpreted with the person’s history, other laboratory measures and clinical context.
Trial findings in generally healthy participants are not the same as evidence in chronic kidney disease, a single kidney, dehydration, acute illness or complex medication use. People taking medicines that affect kidney function or fluid balance need appropriate clinical advice before using supplements. Anyone with diagnosed kidney disease should not rely on marketing claims that creatine is universally safe.
Product quality is another issue. Supplements can differ in purity, labeling and contamination risk. “Creatine” in a trial generally means a defined preparation, most often creatine monohydrate, not every blended product sold online.
Water retention, body weight and gastrointestinal effects
Creatine can increase body weight through water associated with increased muscle creatine stores, especially early in supplementation. That is not the same as fat gain, but it can matter for a person monitoring weight, blood pressure, edema or mobility. A scale cannot distinguish all contributors to a change in weight.
Gastrointestinal symptoms can occur, particularly when a large amount is taken at once. Trials vary in whether they use a loading phase or a lower daily dose. If a product causes persistent diarrhea, nausea, cramping, swelling or another concerning symptom, the appropriate response is clinical review rather than simply changing products.
Older adults may have more medication interactions, dehydration risk and chronic disease than the healthy volunteers in a supplement trial. Safety claims should therefore be scoped to the studied population and duration.
Doses studied versus individualized recommendations
Older-adult trials have used several strategies. Some use a loading phase followed by a lower daily maintenance amount; others use a continuous lower dose. The 2026 postmenopausal-women review found its clearest pooled signal when at least 5 g per day was paired with resistance training, but that is a description of included protocols, not a prescription for every person.
Loading may increase body stores more quickly and may also make early water-weight or gastrointestinal effects more noticeable. A lower daily protocol may reach the same general goal more gradually. The choice can depend on health status, diet, body size, training, product quality and clinician advice.
Readers should not infer that a higher dose is better, that a loading phase is required or that a trial dose is appropriate with kidney disease. A supplement label, medication list and current laboratory context are more relevant to personal decisions than a single pooled average.
Creatine monohydrate versus alternative forms
Creatine monohydrate is the form used in much of the human evidence. Alternative forms are often marketed as more absorbable, more effective or less likely to cause water retention, but a marketing claim is not a head-to-head clinical outcome. If a different form has not been tested in the relevant older-adult population, its evidence base should be treated as thinner.
Product choice should include transparent labeling, independent quality controls where available and avoidance of proprietary blends that conceal amounts. The presence of an ingredient on a label does not show that the finished product matches the dose or purity of a research preparation.
Why creatine is a healthspan or function intervention, not a proven longevity drug
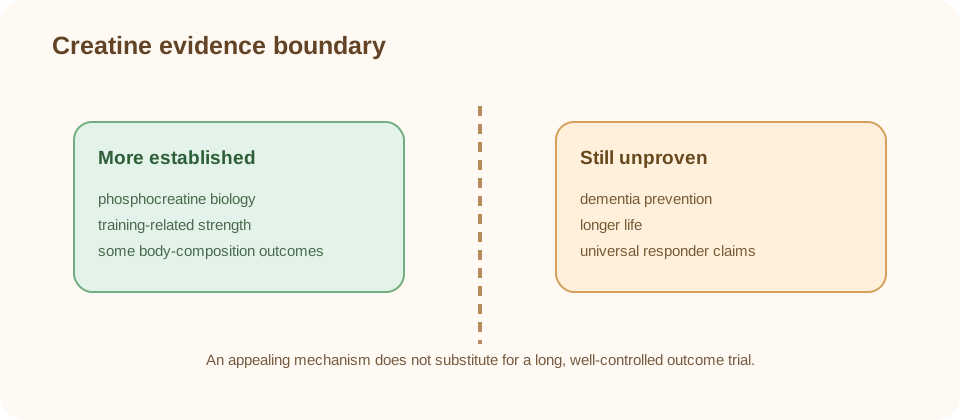
Creatine may help preserve or improve selected measures of muscle function when combined with training. That can be valuable for healthspan because strength and physical capacity are relevant to independence. But the current trials are generally too short, too small and too focused on surrogate or performance endpoints to test lifespan extension.
No credible human evidence shows that creatine delays all-cause mortality, prevents every age-related disease or resets biological age. Animal, cellular and biomarker findings can generate hypotheses, but they do not replace a long-term randomized human outcome trial. Even a future positive functional trial would not automatically establish longer life.
A useful comparison is the planned 2026 creatine older-adult trial page, which should be updated as new registered studies become available. Trial registration, prespecified outcomes and transparent adverse-event reporting are more informative than a supplement’s position in a “longevity stack.”
Evidence verdict and practical evidence hierarchy
Creatine monohydrate has a credible biological rationale and a relatively strong human evidence base for a supplement. In older adults, the most consistent signal is a modest additional benefit for lean mass and selected strength outcomes when creatine is combined with resistance training. Physical-function results are promising but rely on lower-quality and heterogeneous evidence. The 2026 postmenopausal-women review adds cohort-specific support for small lean-mass and leg-press gains while leaving bone density uncertain.
Cognitive evidence is more unsettled. A recent review found mostly positive associations in memory and attention, but only two of six studies were blinded interventions and several studies had poor methodological ratings. Kidney and medication context matters, and trial safety in generally healthy adults should not be generalized to people with kidney disease or acute illness.
The responsible conclusion is consider creatine only as a clearly bounded adjunct to evidence-based exercise and clinical care, while treating cognition and longevity claims as incomplete research questions. The best longevity supplements page compares this evidence with other supplement categories.
- put progressive, safe resistance training at the center of muscle goals;
- read creatine effects as incremental benefits over an exercise program;
- separate lean mass, strength, physical function, cognition and bone outcomes;
- label trial doses as doses studied, not individualized recommendations;
- use extra caution with kidney disease, dehydration and complex medication use;
- do not claim dementia prevention, sarcopenia prevention or lifespan extension without direct evidence.