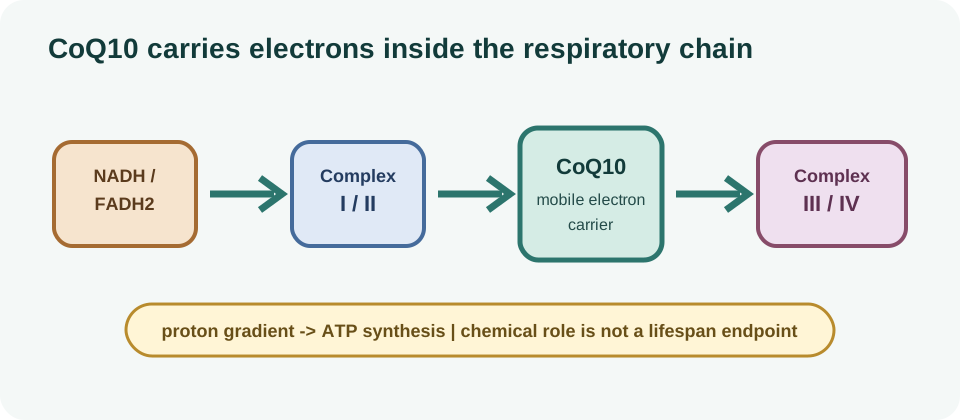
What CoQ10 is: ubiquinone, ubiquinol and electron transport
Coenzyme Q10, usually shortened to CoQ10, is a lipid-soluble molecule found in cell membranes, with particularly important roles in mitochondria. It helps transfer electrons within the respiratory chain and participates in the proton gradient used to make ATP. Its redox forms, ubiquinone and ubiquinol, can interconvert as part of cellular chemistry. The molecule is also discussed as an antioxidant, although antioxidant language does not by itself predict a clinical benefit.
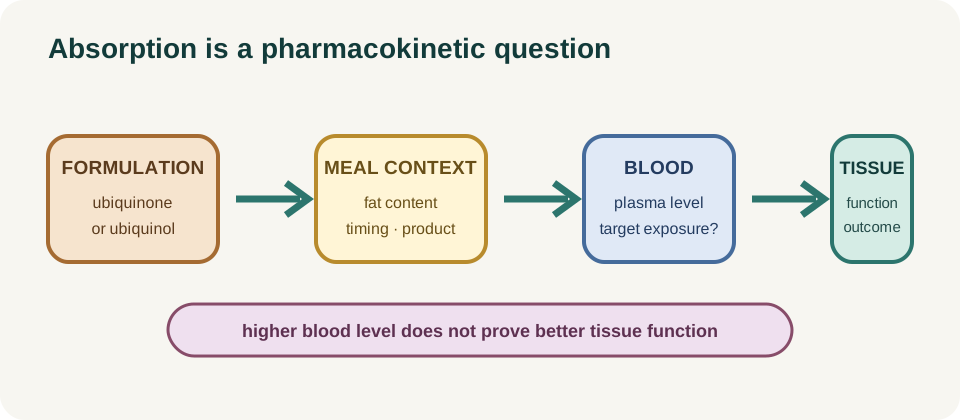
Endogenous CoQ10 is synthesized in the body and is obtained in small amounts from food. Supplements are commonly formulated as ubiquinone or ubiquinol, but formulation, meal timing, fat content, absorption and product quality influence exposure. A formulation that raises a blood measurement is not automatically superior for a specific tissue or outcome.
Because mitochondria are involved in energy metabolism, oxidative stress and physical performance, CoQ10 has an intuitive place in aging discussions. The mechanistic question is reasonable: if availability or redox balance changes with age, could restoring it improve function? The human question is harder: does supplementation improve a meaningful outcome in people who are not CoQ10-deficient?
Why CoQ10 is discussed in aging biology
Some studies report age-related changes in CoQ10 concentration, mitochondrial activity or the ratio between redox forms. These observations are compatible with several explanations: altered synthesis, tissue demand, medication effects, nutrition, illness, oxidative environment or changes in body composition. A lower average level does not prove that every older adult has a correctable deficiency.
That distinction prevents a common reasoning error. A molecule can be essential, decline in some settings and still fail as a universal supplement. The relevant evidence depends on baseline status, tissue, dose studied, duration, disease context and endpoint. The mitochondrial dysfunction aging page describes why a pathway-level rationale must be connected to actual physiology.
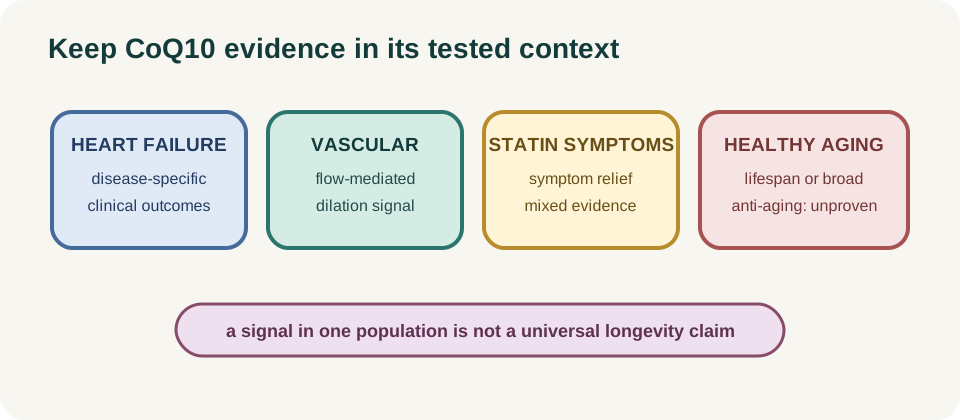
CoQ10 may be more relevant in people with rare biosynthetic disorders, particular medication exposures or disease-specific mitochondrial stress, but “might be relevant” is not a general recommendation. Those groups require clinical assessment. For healthy older adults, the claim that CoQ10 broadly slows aging remains unproven.
| Finding | Reasonable interpretation | What it does not establish |
|---|---|---|
| Higher plasma CoQ10 | the supplement was absorbed into circulation. | higher muscle mitochondrial function or longer life. |
| Higher tissue level | the target tissue was exposed. | improved organ performance or disease outcome. |
| Improved laboratory marker | one measured pathway changed. | global slowing of aging. |
| Symptom improvement | a clinical effect may exist in that population. | that the effect generalizes to healthy adults. |
The 2026 randomized trial in robust older adults
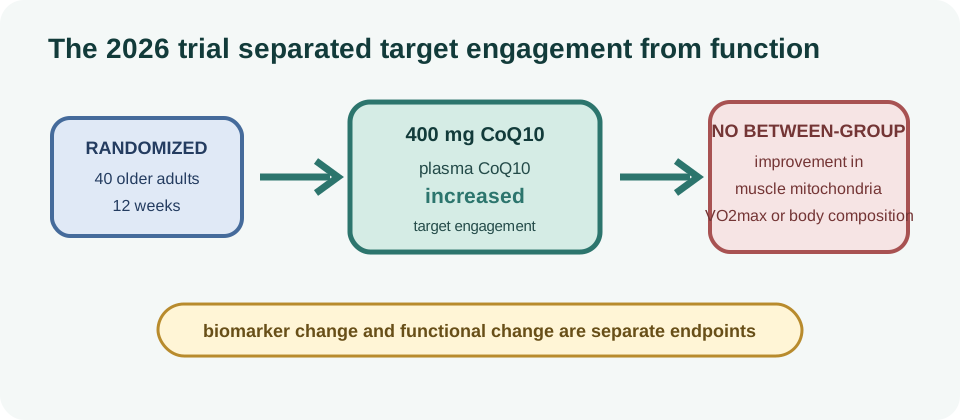
A 2026 double-blind randomized placebo-controlled study enrolled 40 community-dwelling older adults with an average age of about 74 years. Participants received 400 mg of oral CoQ10 daily or placebo for 12 weeks. The investigators measured plasma and muscle CoQ10, mitochondrial respiratory capacity, hydrogen-peroxide emission, mitochondrial content, glucose handling, VO2max, body composition and cognitive outcomes.
Plasma CoQ10 increased significantly, but the study found no between-group improvement in muscle or isolated-mitochondria respiratory capacity, hydrogen-peroxide emission, mitochondrial content or muscle CoQ10. Glucose homeostasis, VO2max and body composition were also unchanged. The result is especially useful because it tests the exact bridge that marketing often assumes: from a higher circulating level to better mitochondrial function.
The study was short and modest in size, so it cannot settle every question. It does show that raising plasma CoQ10 is not sufficient to demonstrate improved mitochondrial function in robust older adults over 12 weeks. One author disclosed consulting for Pharma Nord; the other authors reported no conflict, and the funders reported no role in the study.
Cardiovascular evidence: useful signal, different question
Cardiovascular studies provide some of the more credible reasons CoQ10 remains clinically interesting. A 2024 systematic review and meta-analysis of 12 randomized studies involving 489 participants reported a modest improvement in flow-mediated dilation, with a weighted mean difference of 1.45 and a 95% confidence interval from 0.55 to 2.36. The analysis did not find clear improvement in the measured adhesion molecules VCAM or ICAM.
Flow-mediated dilation is a vascular function measure, not a lifespan endpoint. A modest average change can be biologically interesting while still leaving uncertainty about durability, clinical events, population selection and whether the result is large enough to affect care. The study authors also called for additional research.
This is why cardiovascular evidence should be described as domain-specific. It does not show that CoQ10 reverses aging, prevents all cardiovascular disease or improves mitochondrial function in every older adult. It may justify further trials in selected populations and outcomes.
Q-SYMBIO and chronic heart failure
Q-SYMBIO was a randomized double-blind trial in patients with chronic heart failure, not a general longevity trial. The disease-specific setting matters because heart failure can involve substantial energetic stress and a different risk-benefit calculation from supplementation in healthy adults. The trial examined clinical outcomes under a structured medical protocol, and its findings are often cited in discussions of CoQ10.
Even a positive heart-failure result cannot be extrapolated directly to people seeking longer life without heart failure. It does not establish that CoQ10 prevents aging, extends lifespan or replaces guideline-directed therapy. Disease-specific treatment decisions require clinicians to consider diagnosis, current medicines, kidney and liver function, and interactions.
Selenium plus CoQ10 in older Swedish adults
Long-term Swedish studies of selenium plus CoQ10 in older adults are important but easy to misread. They tested a combination intervention in a population characterized by relatively low selenium status, so the findings cannot be assigned to CoQ10 alone or assumed to apply to populations with different baseline nutrition. Combination studies can generate useful hypotheses while leaving the contribution of each component unresolved.
Follow-up reports have described associations with cardiovascular outcomes, biomarkers or mortality-related measures in selected participants. Those results need to be read with attention to original randomization, subgroup definitions, adherence, baseline status, event counts and the difference between prespecified and exploratory outcomes. A result in a selenium-low Swedish cohort is not a universal longevity trial.
The most defensible conclusion is that nutrient status and context may modify effects. Future trials should test CoQ10 alone and combinations separately, recruit diverse populations, measure baseline status and use patient-important outcomes. Until then, avoid translating the Swedish combination evidence into “CoQ10 extends life.”
Statin-associated muscle symptoms
Statins can be associated with muscle symptoms in some patients, which has made CoQ10 a popular topic. The proposed rationale is that statins may influence a pathway related to CoQ10 synthesis, but the biological story does not determine the clinical answer. Symptoms are heterogeneous and can also reflect exercise, thyroid disease, vitamin status, musculoskeletal conditions, drug interactions or expectation effects.
A 2025 systematic review and meta-analysis evaluated CoQ10 for statin-associated muscle symptoms. The existence of a meta-analysis does not mean the result is uniformly positive; study methods, symptom definitions, adherence and placebo response matter. A patient should not stop a prescribed statin or self-manage severe muscle symptoms based on an online supplement claim.
For possible statin symptoms, the practical question is diagnosis and cardiovascular risk management, not generalized anti-aging. A clinician may review the timing of symptoms, creatine kinase when appropriate, other medicines and alternative lipid-lowering strategies. Not every statin user needs CoQ10, and symptom relief would still not prove a longevity effect.
Frailty, sarcopenia, cognition and fatigue
Frailty and sarcopenia are attractive endpoints because they reflect function rather than a single laboratory value. Yet CoQ10 evidence in these domains is limited and mixed. Trials may differ in age, baseline health, exercise, protein intake, dose studied, duration and whether participants had a deficiency-prone condition. A plausible mitochondrial mechanism does not guarantee measurable strength or mobility improvement.
The 2026 healthy-older-adult trial did not improve VO2max or body composition over 12 weeks. That does not rule out effects in a different population or over a longer period, but it argues against treating the supplement as an established performance or anti-aging intervention. The related sarcopenia and muscle-aging page explains why progressive exercise, nutrition and functional outcomes remain central.
Claims for fatigue or cognition also need careful separation of symptom scales, objective tests and disease populations. A supplement that helps a subgroup with a defined problem is not thereby a general cognitive or longevity enhancer. The relevant endpoint should be named, measured reliably and compared against placebo.
| Claim | Evidence question | Current boundary |
|---|---|---|
| Supports energy | which tissue and which functional test improved? | biochemical role is not a universal performance effect. |
| Helps heart health | which diagnosed population and clinical endpoint? | heart-failure or vascular evidence is not lifespan evidence. |
| Relieves statin muscle symptoms | were symptoms defined and compared with placebo? | evidence is mixed; do not change prescriptions alone. |
| Anti-aging | was healthspan or lifespan measured? | no established broad human longevity benefit. |
Ubiquinone versus ubiquinol and studied doses
Ubiquinone is the oxidized form and ubiquinol is the reduced form of CoQ10. Both occur in human biology and both appear in supplements. Absorption is influenced by formulation and meal context, and blood concentrations do not necessarily indicate equivalent tissue exposure. Product labels therefore do not answer the clinical question by themselves.
Human trials have studied a wide range of doses and durations. The 2026 older-adult randomized trial studied 400 mg daily for 12 weeks; that is a dose studied, not a universal longevity dose or a recommendation. Q-SYMBIO and other disease studies used their own protocols. Comparing milligrams across formulations without comparing exposure and endpoint can be misleading.
Commercial claims often use “more bioavailable” as if it means more effective. Bioavailability is a pharmacokinetic property. Effectiveness requires a reproducible improvement in a meaningful outcome, and safety requires an appropriate population, duration and interaction assessment. This page does not recommend a product or dose.
Safety, tolerability and interaction considerations
CoQ10 is often tolerated, but “natural” does not mean risk-free. Reported adverse effects can include gastrointestinal symptoms, appetite changes, headache, dizziness or sleep disturbance. Products vary in quality, contamination risk and actual content. People taking medicines or managing chronic disease should ask a pharmacist or clinician before adding a supplement.
Potential interaction questions include anticoagulation, blood-pressure treatment, glucose-lowering therapy and medicines with narrow therapeutic windows. The evidence and clinical importance of an interaction can vary, so a blanket internet rule is not reliable. Anyone with new weakness, dark urine, severe muscle pain, allergic symptoms or other concerning effects needs medical attention.
Who might plausibly benefit—and who has unproven benefit
The most defensible candidates for further study are people with a defined disease context, a documented or strongly suspected deficiency-related problem, or a symptom domain tested in a well-designed trial. Even there, benefit should be judged by the relevant clinical endpoint rather than by a marketing claim about cellular energy.
For a robust older adult asking about longevity, the evidence is different. The 2026 trial raised plasma CoQ10 but did not improve mitochondrial function, VO2max or body composition over 12 weeks. That neutral result does not prove that no one can benefit, but it means a universal healthy-aging claim is not supported.
Established healthy-aging measures—physical activity, resistance training, adequate protein and energy intake, sleep, vaccination, blood-pressure control, lipid management and appropriate medical screening—have a stronger practical foundation than chasing an unvalidated mitochondrial supplement score. The creatine and longevity page, omega-3 longevity page and longevity clinical-trials hub help keep adjacent claims separated by evidence level.
What a true CoQ10 geroscience trial would need to show
A serious longevity trial would need a prespecified population, baseline CoQ10 status, a validated formulation, adequate duration, adherence monitoring and randomization against placebo. It would need outcomes that matter: physical function, hospitalization, disability, cognition, quality of life, disease events or survival. Plasma concentration and mitochondrial assays could explain a result, but they would not replace the clinical endpoint.
It should also test whether effects differ by age, sex, medication, disease, nutritional status and mitochondrial phenotype. The trial should be large enough to estimate harms, report null findings and distinguish primary from exploratory endpoints. A change in a biomarker is a mechanistic clue; it becomes a geroscience result only when it is linked to durable function or health outcomes.
- define the biological and clinical target before recruitment;
- measure baseline status and tissue-relevant exposure;
- separate plasma, mitochondrial and functional endpoints;
- prespecify primary outcomes and monitor adverse events;
- test durability, subgroup effects and patient-important benefit;
- avoid interpreting lifespan from short biomarker studies.
Evidence verdict
CoQ10 has a real mitochondrial role and remains a reasonable subject for disease-specific research. Human evidence supports some selected cardiovascular signals and continues to be evaluated for symptom domains. It does not support calling CoQ10 a proven anti-aging or lifespan-extending supplement.
The most informative recent result is also a caution: in robust older adults, 400 mg daily for 12 weeks raised plasma CoQ10 without improving skeletal-muscle mitochondrial function, VO2max or body composition. Q-SYMBIO and selenium-plus-CoQ10 findings belong to their own populations and combination protocols. Statin-symptom evidence remains a clinical question, not a universal indication.
The responsible conclusion is biologically plausible, clinically context-dependent and longevity-unproven. Follow the supplements and molecules hub for evidence-ranked updates, and treat any future large healthy-aging RCT or major safety signal as more important than a new marketing formulation.
- separate mitochondrial rationale from human outcome evidence;
- keep disease-specific findings in their original populations;
- distinguish blood-level change from tissue function;
- label doses as studied, not recommended longevity doses;
- do not interpret CoQ10 as a lifespan estimate or guarantee.