What spermidine is and where it fits in the polyamine pathway
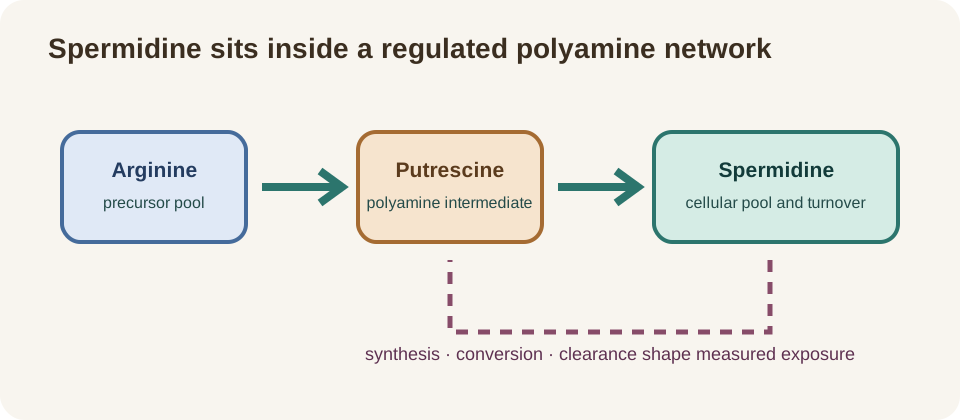
Spermidine is a small polyamine found in bacteria, plants, fungi and animals. Human cells make it through a pathway that begins with amino-acid metabolism and includes putrescine and spermine. Polyamines bind nucleic acids and influence translation, membrane function, ion channels, stress responses and cell growth. They are not a single-purpose “anti-aging switch.”
Cellular levels are controlled by synthesis, uptake, export, conversion and breakdown. That control matters because changing the amount in a meal or capsule does not tell us how much reaches a particular tissue, which metabolites are formed, or whether a relevant pathway changes for long enough to affect function. Blood concentration is an exposure measure, not a direct readout of brain or muscle benefit.
Age-related changes in polyamine metabolism have encouraged the geroscience hypothesis that restoring or supporting spermidine availability might improve resilience. The hypothesis is testable, but the answer may differ by tissue, baseline health, diet, microbiome, renal function, medication and formulation.
Food sources, endogenous production and the age-related question
Spermidine is present in foods including whole grains, legumes, mushrooms, vegetables, soy products and some aged or fermented foods. The amount varies with cultivar, processing, storage and measurement method. Food patterns also deliver fiber, protein, minerals and other bioactive compounds, so an association between a spermidine-rich diet and better health cannot be assigned to spermidine alone.
People also produce polyamines in their own cells and host microbes contribute to the broader intestinal polyamine environment. Intake, absorption, metabolism and tissue handling are therefore different layers of the question. A supplement can standardize the labeled ingredient more readily than a food survey, but standardization does not establish target-tissue exposure or clinical efficacy.
| Exposure | What it can show | What remains uncertain |
|---|---|---|
| Dietary pattern | food intake estimates and overall diet associations. | the independent contribution of spermidine and actual tissue exposure. |
| Plant extract or capsule | administered product, labeled dose and measured blood changes. | product equivalence, organ delivery and durable functional benefit. |
| Endogenous metabolism | polyamine synthesis, conversion and clearance in a person or tissue. | whether changing one pool improves aging outcomes. |
How spermidine may affect autophagy and proteostasis
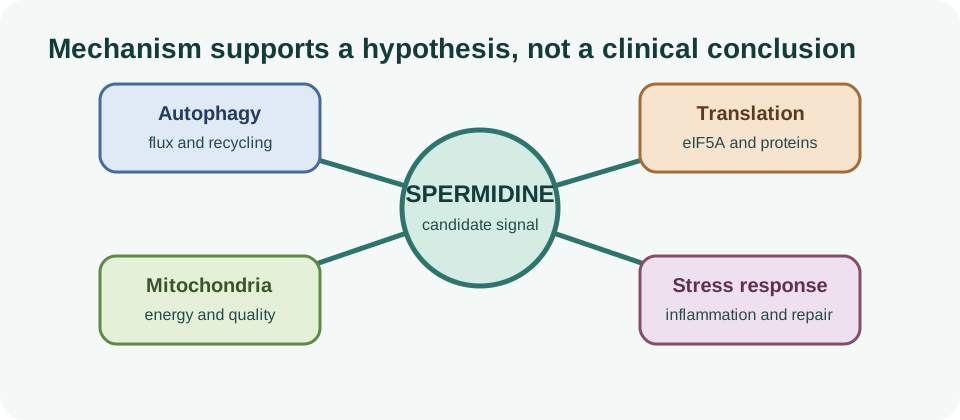
Autophagy is a set of cellular processes that deliver selected material to lysosomes for degradation and recycling. Spermidine has been studied as an autophagy-promoting signal through more than one route, including inhibition of EP300 acetyltransferase activity and effects on translation-related hypusination of eIF5A. These pathways intersect with nutrient sensing, transcription, mitochondrial quality and protein homeostasis.
That mechanism is credible enough to justify experiments, but “autophagy inducer” is not a complete human endpoint. Static LC3, p62, lysosomal proteins or a transcript signature can change because formation increases, degradation slows, cell composition shifts or stress responses are activated. A stronger study measures flux or turnover where feasible and links it to a prespecified tissue function.
The autophagy and longevity page explains why pathway engagement, completed degradation, function and healthspan must remain separate claims. Spermidine should be evaluated with the same discipline.
Mitochondrial, proteostasis and immune-aging effects
Preclinical work links spermidine with mitochondrial respiration, oxidative balance, synaptic maintenance, protein clearance and inflammatory signaling. These effects are biologically related: damaged proteins and organelles can increase cellular stress, while altered metabolism can change the need for recycling. They are not independent proof of a whole-body rejuvenation effect.
The current brain review describes preclinical findings involving mitochondrial fitness, amyloid-related biology, microglial activity and neuroinflammatory signaling. Those findings may identify useful targets for human research, but animal brain exposure, disease models and behavioral tests do not establish prevention of dementia in people. The related proteostasis page and mitochondrial dysfunction page provide the necessary systems context.
There is also a reason to avoid treating every polyamine claim as identical. Spermidine and spermine are interconvertible but have different roles; recent work has explored spermine and ferroptosis biology alongside spermidine-driven autophagy. A product or study that measures one polyamine cannot automatically support a claim about all polyamine functions.
What model-organism lifespan studies show
Foundational work in yeast, worms, flies and mice reported that spermidine can extend lifespan or improve age-related phenotypes under defined experimental conditions. In some models, genetic or pharmacological disruption of autophagy-related machinery weakened those effects. This is valuable causal evidence that cellular maintenance pathways can matter for organismal aging.
It is still not direct evidence that a human supplement extends life. Model organisms differ in dose, metabolism, lifespan, housing, diet, genetic background and disease burden. A lifespan result can also depend on the intervention beginning early, whereas a human product may be used later and alongside many competing exposures.
A 2024 study on fasting and caloric restriction reported that spermidine metabolism participated in autophagy and healthspan-related responses across experimental systems and in human volunteers. Its mechanistic contribution is important, but it does not validate a universal fasting schedule or prove that oral supplementation reproduces every fasting effect.
Observational human evidence: suggestive, not causal
Population studies have associated higher estimated dietary spermidine intake or higher circulating polyamine measures with healthier aging, lower cardiovascular risk or better cognitive outcomes in some cohorts. These signals are consistent with the hypothesis, but they are vulnerable to confounding and reverse causation. People who eat more whole grains, legumes and vegetables may also exercise more, smoke less, have different income and education, or receive better preventive care.
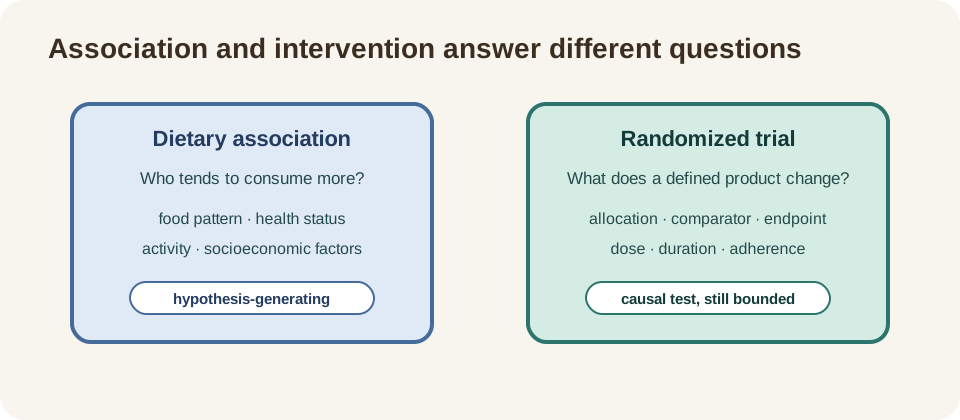
Dietary questionnaires are another limitation. They estimate intake from food-composition tables and may not capture cooking, portion size, supplements, regional foods or laboratory variation. Even a well-adjusted association cannot show that raising spermidine alone will produce the observed outcome.
The 2025 cognition review and a later 2025 review of observational and interventional studies are useful precisely because they place associations beside trials. They describe a biologically plausible compound and encouraging signals, while the intervention literature remains small and heterogeneous. The correct summary is “worth testing,” not “proven to preserve cognition.”
The early 3-month cognition pilot
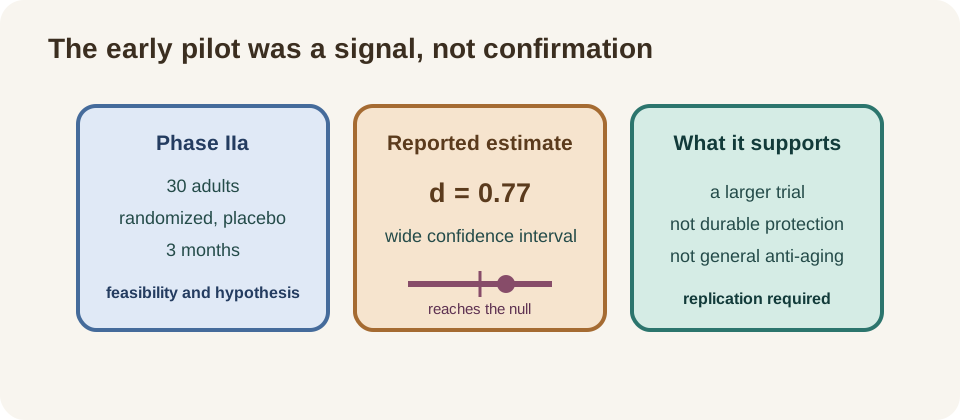
The first SmartAge phase IIa pilot randomized 30 cognitively intact adults aged 60–80 years with subjective cognitive decline to a spermidine-rich plant extract or placebo for three months. The study focused on a mnemonic-similarity measure and emphasized effect-size interpretation. The reported contrast favored the intervention at follow-up, with a mean contrast of 0.17 and a wide 95% confidence interval from −0.01 to 0.35; the reported Cohen’s d was 0.77 with a confidence interval extending from 0 to 1.53.
This was a small pilot, so the result was useful for feasibility and hypothesis generation. A confidence interval that reaches the null is compatible with little or no effect, as well as with a potentially meaningful effect. The study could not establish durable cognitive protection or a general anti-aging benefit.
Other early reports in older adults with dementia used different settings, doses, food preparations and cognitive measures. They are not a clean replication of the phase IIa pilot. Differences in population and design are reasons to compare studies carefully, not to pool their most favorable numbers informally.
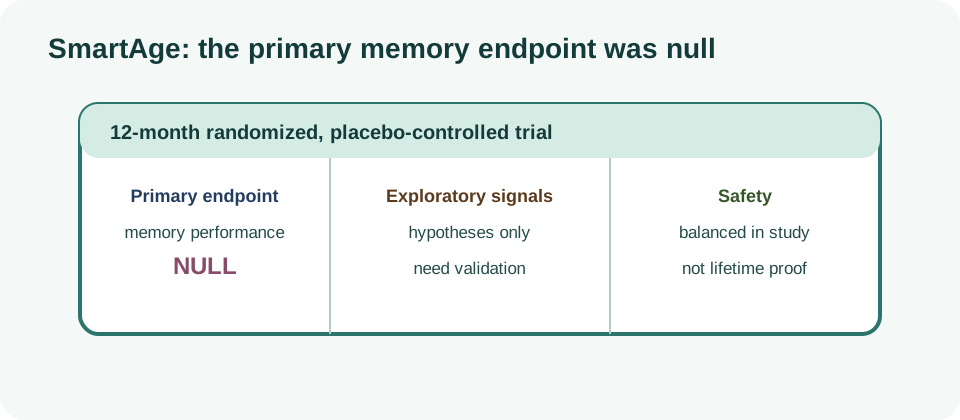
SmartAge 12-month randomized trial: the primary endpoint was null
The best-known human test enrolled 100 adults aged 60–90 years with subjective cognitive decline in a 12-month randomized, double-masked, placebo-controlled phase 2b trial. Participants received a spermidine-rich wheat-germ extract providing 0.9 mg spermidine per day or placebo; 89 participants completed the intervention.
The prespecified primary outcome was change in memory performance measured by mnemonic discrimination. The intention-to-treat analysis found no significant between-group improvement: the difference was −0.03, with a 95% confidence interval of −0.11 to 0.05 and P = .47. Secondary neuropsychological, behavioral and physiological outcomes were also not significantly changed in the main analysis. Adverse events were balanced between groups.
The authors reported exploratory signals involving verbal memory and inflammation, but those findings were not the primary endpoint and require validation. They should not be promoted as proof that the supplement worked when the main memory test did not show a significant benefit. The trial also disclosed commercial relationships involving investigators and the product-associated company. That does not invalidate the study, but it makes independent replication and transparent reporting especially important.
| Finding | Supported interpretation | Unsupported leap |
|---|---|---|
| Primary memory endpoint | no significant improvement versus placebo at 12 months. | spermidine preserves memory in older adults. |
| Exploratory signals | hypotheses about verbal memory or inflammation. | confirmed cognitive or anti-inflammatory efficacy. |
| Safety | adverse events were balanced in this study and period. | long-term safety for every person or product. |
| Dose studied | 0.9 mg spermidine per day in the trial extract. | a personal dose recommendation. |
What the 2025 and 2026 reviews add
The 2025 Ageing Research Reviews article emphasizes autophagy, mitochondrial protection, synaptic maintenance and other mechanisms relevant to cognition. The 2026 npj Aging review frames spermidine as a natural metabolite whose levels may decline with aging and argues for better clinical translation. The 2026 brain review summarizes encouraging preclinical findings and limited, variable human intervention evidence.
These are context-setting reviews, not new large efficacy trials. Their value is to organize mechanisms, observational evidence and clinical gaps. Across them, the same boundary remains: human evidence is not yet large, long or consistent enough to support a claim that spermidine supplementation slows human aging or prevents dementia.
A separate 2025 review of cognitive aging studies helps explain why the evidence can look contradictory. It brings together observational reports, small interventions and the null SmartAge result. A review can identify patterns, but if the underlying trials differ in extract, dose, population, endpoint and duration, a confident pooled estimate may still be inappropriate.
- Mechanism reviews organize plausible pathways but do not establish efficacy.
- Observational studies describe associations and can be confounded by the wider diet and health pattern.
- Randomized trials test a defined product, dose, population and prespecified endpoint.
- Null primary endpoints remain part of the evidence even when exploratory signals look promising.
The 2025 autophagy biomarker proof-of-concept
A 2025 proof-of-concept pilot examined a spermidine-rich rice-germ extract in relation to biomarkers of healthy aging and autophagy. This type of study addresses an important translational question: can a defined product change a measurable human biology signal? It does not by itself answer whether participants think better, remain independent longer, experience fewer diseases or live longer.
Biomarker interpretation requires attention to assay validity, tissue or sample type, timing, comparator, adherence, multiplicity and product composition. An autophagy-related signal may reflect pathway engagement without proving completed flux, and a short study cannot establish durability. Product-specific findings should not be generalized to every spermidine capsule or dietary pattern.
The pilot is therefore best treated as a bridge-building study. It can help select biomarkers and design a larger trial, especially if it reports target engagement clearly. The next study should connect the biomarker to a prespecified functional outcome and independently reproduce the finding.
| Layer | Example question | What it cannot establish alone |
|---|---|---|
| Exposure | did the product change measured spermidine or a related metabolite? | benefit in the target organ. |
| Pathway | did an autophagy-related marker or flux measure change? | better cognition, function or survival. |
| Clinical outcome | did a prespecified patient-important endpoint improve? | lifespan extension without long follow-up. |
Doses and forms studied: reporting, not recommending
Human research has used different preparations and amounts. The SmartAge 12-month trial used a wheat-germ extract providing 0.9 mg spermidine per day. The three-month pilot used a spermidine-rich plant extract, while nursing-home reports used dietary changes or higher estimated intake under different conditions. A registered cardiovascular trial protocol has also proposed a substantially different daily exposure. These numbers cannot be compared as though they were the same product, dose, population or endpoint.
Labels may report spermidine content, total polyamines, plant-extract amount or an amount estimated from a source ingredient. Extraction, stability, analytical method, batch variation and co-ingredients affect comparability. A higher labeled amount is not automatically more effective, and the dose with the best biomarker response is not necessarily the dose with the best safety or clinical outcome.
Why dietary intake and supplement exposure are not interchangeable
A diet supplies spermidine within a food matrix and alongside many other nutrients. A supplement can deliver a concentrated extract or isolated ingredient at a more repeatable labeled amount. Those exposures may differ in absorption, timing, co-metabolites, gut effects and batch composition. A person who eats more legumes is not conducting the same intervention as a participant taking a standardized capsule.
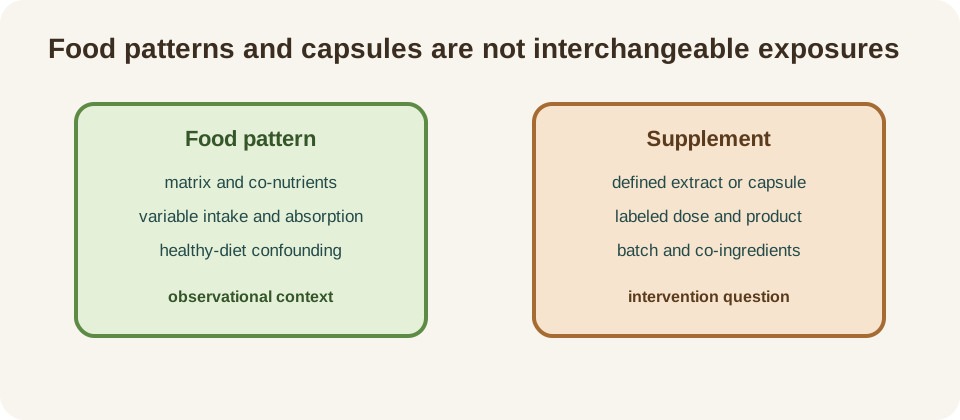
There is also a causal-direction problem. If healthier people eat a more varied diet and happen to consume more spermidine, the observed association may be a marker of the whole pattern. If illness changes appetite and diet, low intake may be a consequence rather than a cause. Randomization helps with these problems, but only if the randomized intervention is adequately dosed, well characterized and followed for a meaningful endpoint.
For brain outcomes, the barrier between blood and brain adds another layer. Animal work can demonstrate brain exposure under experimental conditions; a human blood measurement does not prove equivalent neuronal or glial exposure. The brain aging page covers this translation problem, while inflammaging helps distinguish inflammatory biomarkers from clinical protection.
What spermidine has not shown
Spermidine has not been shown in a definitive human trial to extend lifespan, reverse biological aging, prevent dementia, restore memory across older adults, or induce beneficial autophagic flux in every relevant tissue. It has not been established that a particular commercial product reproduces model-organism findings in humans. Nor does a favorable secondary outcome overturn a null primary endpoint.
That list is not a dismissal of the molecule. It is the boundary that keeps a promising research program credible. A compound can be safe enough for further study, biologically active, and potentially useful for a subgroup while still lacking evidence for broad public health claims.
Evidence verdict and trials still needed
Spermidine remains one of the more interesting nutrition-linked geroscience candidates because it connects endogenous metabolism, autophagy, translation, mitochondria and brain-aging hypotheses. Model organisms provide meaningful causal evidence, and observational human studies provide a coherent reason to continue research. But the 12-month SmartAge trial did not improve its primary memory endpoint, and newer reviews continue to describe the human record as limited and heterogeneous.
The next generation of trials should use chemically and analytically characterized products, prespecified primary outcomes, adequate sample sizes, independent replication and transparent funding statements. They should measure exposure and adherence, use validated functional outcomes, report adverse events carefully, and include enough follow-up to distinguish transient biomarker movement from durable benefit.
- compare a defined product against placebo with a prespecified primary endpoint;
- separate dietary pattern, extract exposure and isolated spermidine;
- pair pathway or flux measures with cognition, function or another patient-important outcome;
- test whether findings replicate across age, sex, baseline function and relevant disease risk;
- retain null, subgroup and contradictory results in the permanent evidence record.