What apigenin is and where it occurs
Apigenin is a naturally occurring flavone, a type of polyphenol. It is present in parsley, celery, chamomile, some herbs and other plant foods. In plants it is often found as glycosides, in which the flavone is attached to a sugar or related group. That chemical context affects how the compound is released, absorbed and metabolized.
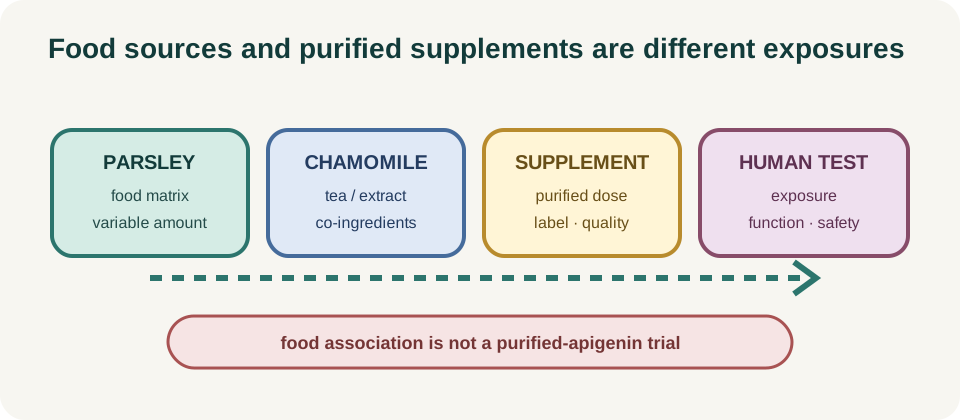
Food exposure and a purified supplement are not automatically equivalent. A meal delivers a mixture of compounds, fibre, fat, water and other constituents. A capsule can deliver a concentrated nominal amount in a different chemical form. Human tissues then encounter parent apigenin, glucuronides, sulfates and other metabolites rather than a simple unchanged molecule. A claim about one preparation should not be generalized to every tea, extract or supplement.
Apigenin is discussed in longevity because it touches several pathways involved in metabolism, inflammation, sleep and cellular stress. Those connections are useful for hypothesis generation. They are not a human anti-aging verdict. The NAD metabolism and aging page explains why changing a cofactor pathway is different from demonstrating durable improvement in function or disease outcomes.
Why apigenin entered longevity discussions
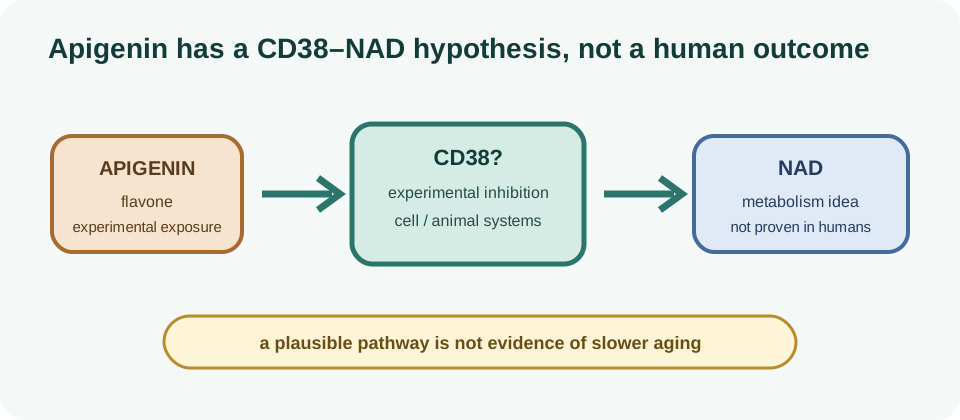
The central hypothesis is that aging changes the balance between NAD+ production and consumption. NAD+ supports metabolism and serves as a substrate for enzymes involved in cellular regulation and repair. CD38 is a multifunctional enzyme that consumes NAD+. Some animal and tissue studies report higher CD38 activity or expression with age and lower NAD+ availability. That makes CD38 an attractive research target.
Apigenin became interesting because laboratory work suggested it can inhibit CD38 and alter the NAD+/NADH and SIRT1-related signaling environment. The resulting narrative is easy to compress into “apigenin raises NAD.” That wording skips the essential questions: in which tissue, at what exposure, in which chemical form, for how long, and with what clinical result?
A 2025 review describes CD38 as a potential therapeutic target and lists small-molecule inhibitors as an area for future anti-aging research. A review is a map of a field, not a clinical efficacy trial. The review’s existence supports continued investigation; it does not validate apigenin supplementation for healthy adults.
CD38 and age-associated NAD decline
CD38 is not simply an unwanted “NAD drain.” It has physiological roles in calcium signaling, immune biology and other processes. Enzyme activity is distributed across cell types and tissues, and the effects of changing it may depend on disease state and timing. Suppressing one route of NAD consumption could have different consequences from changing total NAD in blood or one experimental tissue.
NAD+ itself is also compartmentalized. A measured concentration in blood or a homogenized tissue does not necessarily represent the pool available to a particular nucleus, mitochondrion or immune cell. Age-related differences may reflect inflammation, cell composition, metabolism, diet, medication or organ function. Restoring an average value is not automatically equivalent to restoring youthful physiology.
The practical reading rule is pathway plausibility is not pathway proof. A credible human study would need a reproducible apigenin exposure, validated pharmacodynamic measures, appropriate tissue or cell targets, a comparator and outcomes that matter to participants.
| Observation | What it may support | What it does not prove |
|---|---|---|
| CD38 rises in an aging model | CD38 may be involved in that model’s NAD biology | CD38 is the only cause of human NAD decline |
| Apigenin inhibits CD38 in vitro | experimental target engagement is plausible | a safe human dose or tissue effect |
| NAD changes in an animal | the pathway can be manipulated in that model | human longevity or healthspan benefit |
| A supplement raises a blood metabolite | absorption occurred | senescence reversal or clinical improvement |
What experimental apigenin studies actually show
Cell studies have reported that apigenin can inhibit CD38 activity and influence the SIRT1-NAD+-CD38 axis. One cellular-senescence study linked apigenin exposure with changes in NAD-related signaling and reduced markers of oxidative-stress-induced senescence. Such work can identify a mechanism worth testing. It uses concentrations, cell types and exposure conditions that may not match human supplementation.
Other experimental studies have reported changes in inflammatory signaling, cancer-cell proliferation, neuronal stress, learning or sleep-related behavior. These outcomes are biologically diverse. A result in a cultured cell or a mouse brain does not establish that an oral product reaches the corresponding human compartment, and a sleep-like behavioral change in an animal is not evidence of improved human sleep or slower aging.
The evidence should be staged rather than averaged into a marketing score. Mechanistic studies answer whether a target can be affected. Animal studies answer whether a model phenotype changes. Human pharmacokinetic studies answer whether an exposure occurs. Randomized human outcome trials answer whether a defined intervention improves health. Apigenin has evidence in the first and third categories, but no established human longevity result.
Animal longevity and neurodegeneration models
Animal research is part of apigenin’s appeal. Reports summarized in the sleep-and-aging review include improved learning or memory in older mice, effects in cancer xenograft models, sedative-like effects in rodents, longer survival in some fly models of neurodegeneration and lifespan effects from apigenin glycosides in worms.
These findings are useful for identifying candidate pathways and deciding what to test next. They do not show that apigenin extends human life. Species differ in absorption, metabolism, lifespan, dosing feasibility and disease biology. A model can show a large molecular response at an exposure that is not achievable or safe in people.
Animal studies also need to be interpreted by endpoint. A mouse learning task, a worm lifespan curve, a fly survival experiment and a human cognitive test are not interchangeable measures. If an animal result is presented as “anti-aging,” ask which organism, tissue, dose, control, duration and outcome were used. A broad label cannot substitute for those details.
Human pharmacokinetics: parent compound versus metabolites
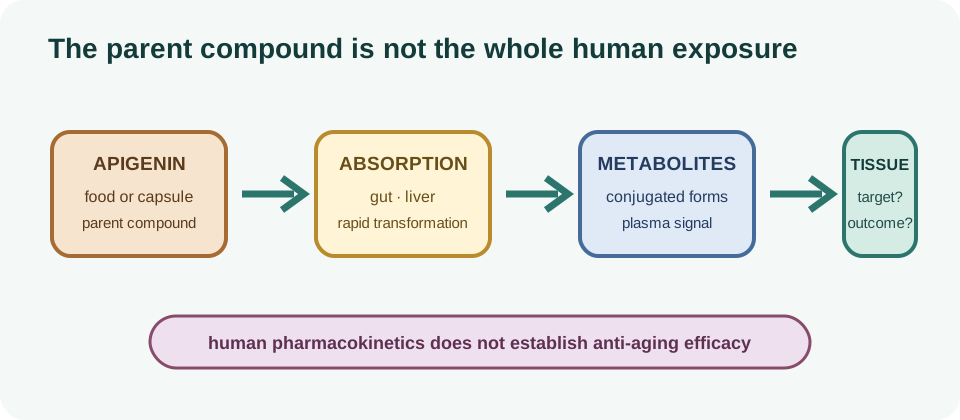
The most informative human apigenin evidence is pharmacokinetic rather than longevity evidence. A 2022 study examined absorption, distribution, metabolism and excretion of apigenin and its glycosides in healthy male adults. The investigators identified apigenin-4′-glucuronide, apigenin-7-glucuronide and apigenin-7-sulfate as in-vivo metabolites.
Free apigenin was poorly absorbed in the study’s conditions, with metabolites equivalent to about 0.5% of the intake excreted in urine after a purified exposure. The food matrices behaved differently. A parsley drink produced a metabolite peak around four hours and urinary excretion equivalent to 11.2% of intake; parsley powder with yogurt extended the peak to about six hours; chamomile tea produced a peak around two hours and urinary excretion equivalent to 34% of intake. These values describe one small acute study and its tested preparations, not universal absorption rates.
The study shows why “apigenin dose” is incomplete without chemical form and matrix. It also shows why a cell experiment using the parent compound cannot be transferred directly to a human result measured mainly through metabolites. Whether those metabolites inhibit CD38 in the relevant human tissue, and whether that changes aging-related function, remains unresolved.
Chamomile, apigenin-containing foods and attribution
Chamomile is often used in discussions of apigenin because it contains apigenin glycosides and has a long history as a tea or extract. Human studies of chamomile may report changes in anxiety, mood, pain or sleep-related outcomes. Those findings can be relevant to a chamomile preparation in a particular population. They are not purified-apigenin trials.
A plant extract contains multiple constituents, and the behavioral outcome may involve several pathways. The preparation, dose, extraction method, comparator, blinding and outcome instrument all affect interpretation. A positive chamomile result cannot isolate apigenin, and a null result does not disprove a purified-apigenin mechanism.
The same issue applies to dietary surveys. If higher intake of apigenin-containing foods correlates with better sleep or health, the association may reflect the overall diet, socioeconomic factors, physical activity, alcohol use, illness, medication, sleep schedule or other plant compounds. Observational intake is not a randomized apigenin intervention.
Sleep claims and the aging connection
Sleep is relevant to healthy aging, but the relationship is bidirectional and multifactorial. Poor sleep can accompany pain, mood disorders, sleep apnea, medications, shift work and cardiometabolic disease. Improving sleep can be valuable even when it has nothing to do with changing CD38 or NAD+.
The 2024 review on apigenin at the intersection of sleep and aging summarizes animal and human-context evidence, including sedative-like effects in experimental models and observations around chamomile or dietary intake. The authors also identify the need for human studies that measure established aging-related biomarkers, cardiometabolic health, motor function and cognition. That qualification is important: the review does not establish a purified-apigenin sleep or longevity treatment.
People should not use an apigenin supplement as a substitute for evaluation of persistent insomnia, loud snoring, witnessed apneas, severe daytime sleepiness or a major change in mood. Nor should a sleep benefit, if one occurs, be narrated as proof of slowed aging. Sleep is a meaningful outcome in its own right, but it is not a validated proxy for human lifespan.
- separate sleep symptom relief from longevity claims;
- identify whether the study used chamomile, food or purified apigenin;
- check the sleep measure, comparator and follow-up;
- evaluate persistent sleep problems clinically.
Bioavailability and formulation uncertainty
Apigenin has low and variable oral bioavailability, and reviews describe extensive metabolism and possible interaction with drug-metabolizing enzymes and transporters. Formulators may attempt to improve solubility, stability, absorption or tissue delivery. That can create a new pharmacokinetic intervention rather than simply making a familiar food compound “stronger.”
Higher exposure can increase both the chance of a desired effect and the chance of an interaction. A formulation that produces a larger plasma signal still needs human evidence of a meaningful benefit. It also needs a safety study at the same preparation, dose and duration. Relative bioavailability is not a surrogate for longer life.
Comparisons should therefore report the product’s chemical form, analytical verification, delivery system, fed or fasted condition, measured parent and metabolite exposure, and the endpoint that the formulation is intended to improve. Without that information, products described as “high bioavailability” cannot be compared responsibly.
Safety and interaction uncertainty
Apigenin occurs in foods, but concentrated supplementation can produce an exposure profile that differs from ordinary diet. Human safety data at chronic supplemental exposures are limited. The absence of a serious event in a short pharmacokinetic study should not be interpreted as proof of long-term safety in older adults, people with chronic disease or people taking multiple prescriptions.
Experimental and pharmacokinetic literature raises the possibility of interactions through enzymes and transporters, including pathways involved in drug metabolism. The clinical importance depends on the medicine, dose, formulation, tissue exposure and the person’s physiology. Anyone taking anticoagulants, immunosuppressants, sedatives, cancer treatment or medicines with a narrow therapeutic range should ask a pharmacist or clinician before using a concentrated apigenin product.
Apigenin may also have sedative or biologically active effects that are undesirable in some contexts. “Natural” does not mean inert, and a product marketed for sleep may add to other sedating substances. This page does not recommend a supplement dose for sleep, NAD support or longevity.
Apigenin versus NAD precursors
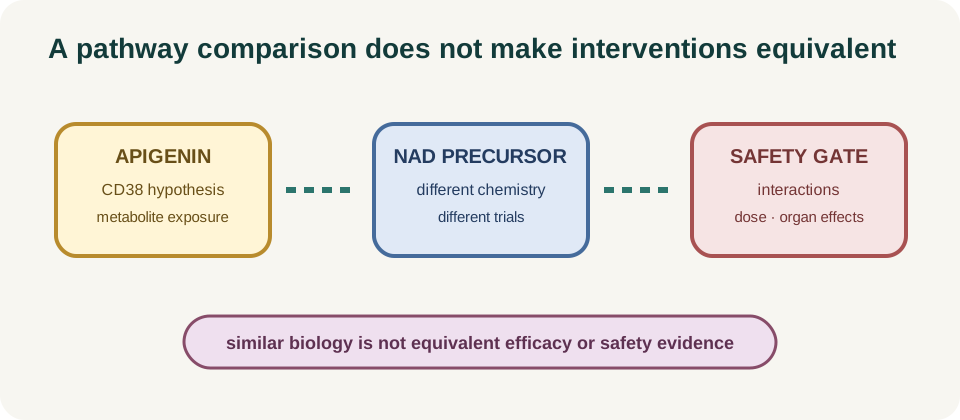
Apigenin and NAD precursors address different parts of the hypothesis. Apigenin is discussed as a possible inhibitor of an NAD-consuming enzyme, especially CD38. NMN and NR are precursors intended to supply building blocks for NAD-related metabolism. Neither category has a universal human longevity verdict, and combining them does not automatically create a validated strategy.
The human evidence bases are also different. Apigenin’s most direct human study described absorption and metabolites in a small acute setting. NAD-precursor research includes a larger and more developed set of human trials and reviews, but those studies still vary in tissue, dose, duration and clinical outcome. A 2026 systematic review of NAD supplementation can provide context for how precursor evidence is judged; it should not be used to transfer precursor findings onto apigenin.
The NMN and longevity page and NR and longevity page separate precursor-specific evidence from broader NAD biology. Apigenin should be held to the same standard: name the intervention, measure exposure and target engagement, prespecify meaningful outcomes and follow participants long enough to detect benefit and harm.
| Question | Apigenin | NMN or NR |
|---|---|---|
| Proposed action | experimental inhibition of NAD-consuming CD38 | precursor supply for NAD-related metabolism |
| Most direct human evidence | absorption, metabolism and food-matrix differences | human pharmacokinetic and intervention studies |
| Human longevity proof | not demonstrated | not established as lifespan extension |
| Key uncertainty | tissue exposure, metabolites and interactions | clinical relevance, durability and long-term safety |
Evidence verdict and what human proof would look like
Apigenin has a coherent experimental rationale: CD38 can consume NAD+, age-related CD38 changes are biologically plausible, and apigenin can inhibit CD38 in selected laboratory systems. Those observations do not show that apigenin raises NAD+ in the relevant human tissue, reverses senescence, improves healthspan or extends life.
The human pharmacokinetic study is valuable because it demonstrates that parent apigenin is poorly absorbed under the tested conditions and that glycoside form and food matrix strongly change metabolite profiles. Chamomile and dietary findings provide context but cannot isolate apigenin. Human sleep or mood observations, even when useful, should not be inflated into a longevity claim.
The responsible conclusion is mechanistically interesting, human longevity evidence absent. A credible next step would be a randomized human study of a reproducible apigenin preparation with pharmacokinetic and pharmacodynamic measures, a prespecified clinical or functional outcome, a credible comparator, interaction monitoring and follow-up beyond the dosing window. A higher blood metabolite or an animal lifespan result would not be enough.
For updates, follow the supplements hub, the research hub, the cellular senescence page and the biological-age test guide. The page should be updated if a purified-apigenin randomized human aging or NAD trial reports results.
- keep CD38 and NAD mechanisms separate from human outcomes;
- treat parent apigenin and metabolites as different evidence questions;
- do not use chamomile studies as purified-apigenin proof;
- read sleep and food associations as context, not lifespan evidence.